
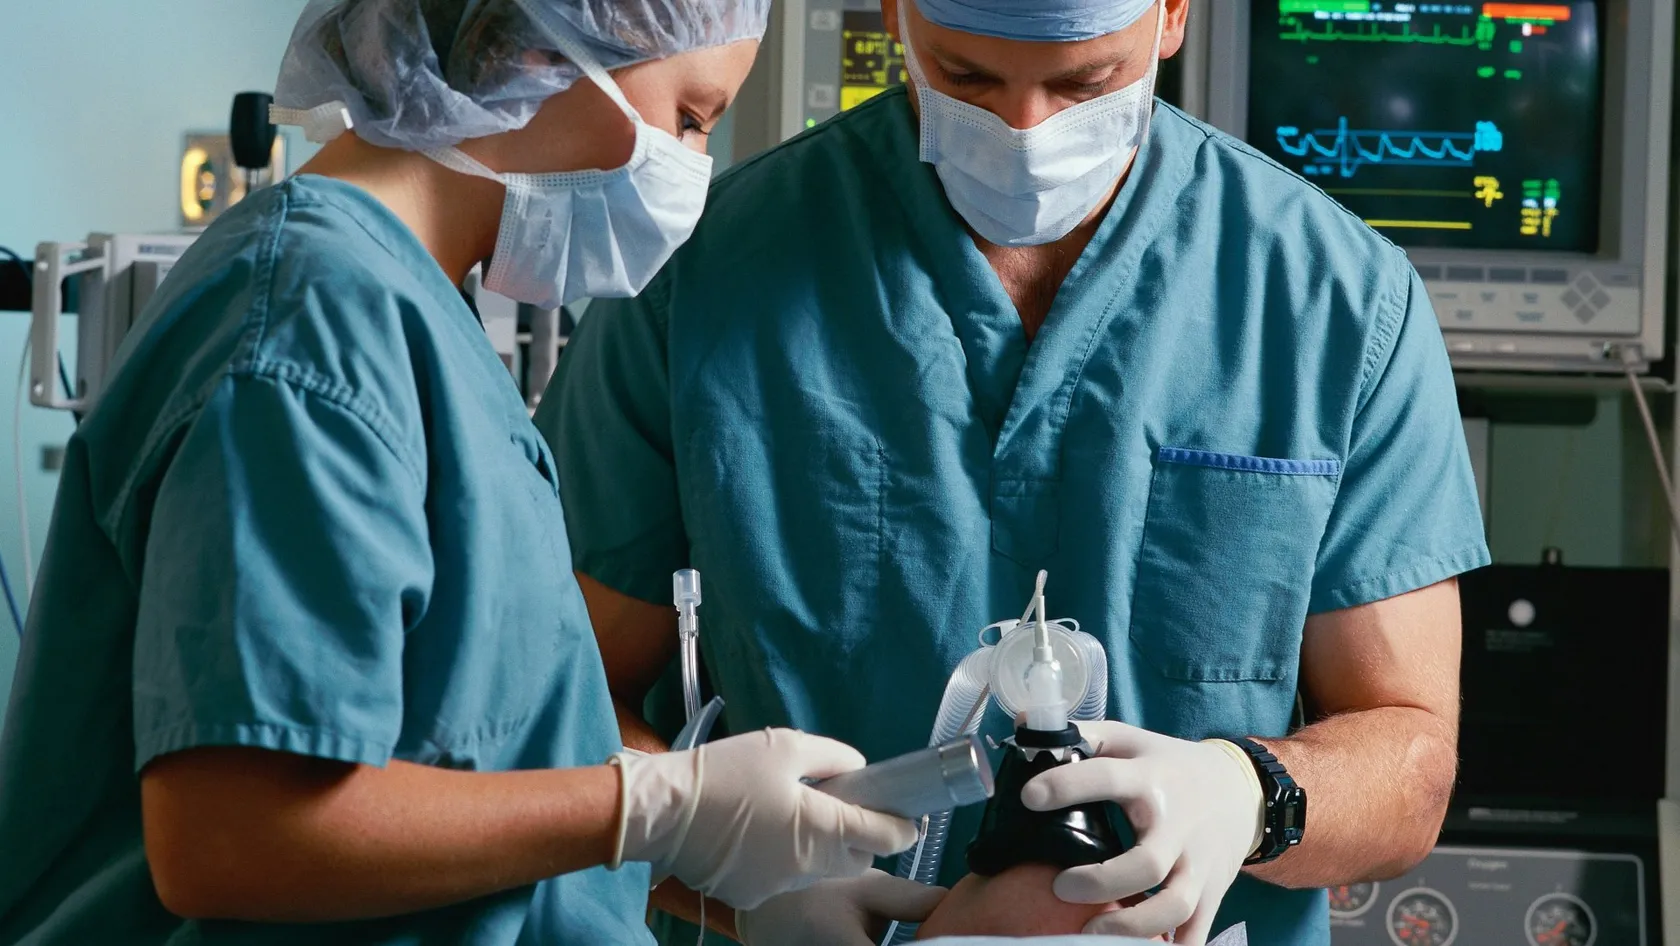
Stereotactic Radiosurgery - SRS
Stereotactic radiosurgery treats brain metastases, vestibular schwannoma, meningioma, arteriovenous malformation and trigeminal neuralgia with focused radiation in one to five sessions, without an incision or a night in hospital. It covers how it compares with open surgery and whole brain radiation, what the randomized trials show about memory and survival, the treatment day step by step, radiation necrosis and other risks, the MRI follow-up, and how patients from abroad arrange it in Istanbul.
About This Department
Radiosurgery is not surgery. Nothing is cut. A high dose of focused radiation treats a brain tumor in one session, and the patient goes home the same day. The word stays because the result resembles one.
Stereotactic radiosurgery, or SRS, aims dozens of narrow radiation beams at a target in the brain from different directions so that they overlap only at the tumor, and delivers in one to five sessions a dose that a conventional course would spread over weeks. In the randomized trial that changed practice, patients with one to three brain metastases treated by radiosurgery alone had less cognitive decline at three months than those who also received whole brain radiation, 63.5 percent against 91.7 percent, with the same survival (Brown and colleagues, JAMA, 2016). A Japanese study of 1,194 patients then showed that up to ten metastases can be treated the same way (Yamamoto and colleagues, Lancet Oncology, 2014). This page explains what radiosurgery treats, how it compares with open surgery and whole brain radiation, what the evidence shows, what the treatment day is like, the risks and the follow-up, and how patients from abroad arrange it at Biruni Hospital in Istanbul.
What radiosurgery is
A single beam of radiation strong enough to destroy a tumor would damage everything on its path. Radiosurgery solves this by using many weak beams. Each passes through healthy brain at a dose it tolerates, and all of them meet at the target, where the dose adds up to something no tumor survives. The beams stop at the edge of the target within a millimeter or two. A tumor next to the optic nerve or the brainstem can therefore be treated with the nerve left intact. The Versa HD accelerator at Biruni Hospital delivers it through a fine collimator and a mask molded to the patient's face, without a frame screwed to the skull.
No patient sustained significant perioperative morbidity. The average duration of hospital stay was less than one day. Tumor control rates at ten years were 97 percent (Lunsford and colleagues, Journal of Neurosurgery, 2005).
That series treated benign tumors of the hearing nerve on a Gamma Knife over fifteen years in Pittsburgh. The hospital does not have a Gamma Knife. It delivers the same doses to the same targets on a linear accelerator, which the radiosurgery community has done for three decades with published results that match, and which also treats larger targets and targets outside the head that a Gamma Knife cannot reach.
What it treats
Small, well-defined targets. Under three centimeters as a rule, or up to four in a few sessions.
- Brain metastases. The commonest reason. One to ten deposits from a lung, breast, kidney, skin or bowel cancer, treated in one session while the primary cancer is treated with drugs.
- Vestibular schwannoma. A benign tumor of the hearing and balance nerve, where radiosurgery stops growth in nearly all cases and preserves hearing more often than surgery.
- Meningioma. Benign tumors of the brain covering, when surgery would be risky or has left residual tumor.
- Arteriovenous malformation. A tangle of abnormal vessels that can bleed. Radiosurgery closes it over two to three years.
- Trigeminal neuralgia. Facial pain from a compressed nerve, where a single dose to the nerve root relieves pain in most patients within weeks.
- Pituitary adenoma and other rare tumors. Residual or recurrent tumors near the optic nerves, and selected tumors of the spine treated with the same technique.
| Target | Sessions | What to expect |
|---|---|---|
| Brain metastasis under 2 cm | 1 | Local control in about nine of ten at one year |
| Brain metastasis 2 to 4 cm, or near the brainstem | 3 to 5 | The dose is split to protect the tissue around it |
| Vestibular schwannoma | 1, or 3 to 5 for larger tumors | Growth stops. The tumor shrinks slowly over years |
| Meningioma | 1 to 5 | Growth stops in the great majority |
| Arteriovenous malformation | 1 | Closure over two to three years, with yearly MRI |
| Trigeminal neuralgia | 1 | Pain relief in weeks to months |
Some targets go to surgery instead. A tumor larger than four centimeters, a tumor causing pressure that must be relieved at once, and a cancer whose diagnosis is not yet certain, because radiosurgery removes no tissue and gives the pathologist nothing to examine, and a treatment plan for a brain tumor whose type is unknown is a plan built on a guess.
Radiosurgery, surgery or whole brain radiation
Three tools. Each has a job.
How the choice is made
Open surgery removes a large tumor, relieves pressure and provides a diagnosis, at the cost of a craniotomy, days in hospital and a recovery of weeks, and it is often followed by radiosurgery to the cavity to stop regrowth. Whole brain radiation treats the whole organ over two weeks and catches deposits too small to see. Its price is hair loss, tiredness and a measurable decline in memory and attention, documented in the trials below. Radiosurgery treats what can be seen, in a day, with no recovery. It leaves the rest of the brain untouched, so new deposits can appear later and the MRI has to be repeated to catch them. For a patient with a handful of metastases and a cancer that is otherwise under control, radiosurgery has become the standard, with whole brain radiation kept for patients with many small deposits or a cancer that seeds the brain diffusely. The decision is made in a tumor board with the neurosurgeon, the medical oncologist and the radiation oncologist in the same room.
What the trials show
The question was never whether radiosurgery controls the tumors it treats. It was whether leaving the rest of the brain untreated costs the patient anything.
Does skipping whole brain radiation shorten life?
Up to ten
The Japanese study enrolled 1,194 patients with one to ten new brain metastases at 23 centers and treated every one of them by radiosurgery without whole brain radiation. Survival in the 208 patients with five to ten tumors was 10.8 months, exactly the same as in the 531 with two to four, and serious side effects occurred in 2 to 3 percent of each group (Yamamoto and colleagues, 2014). Count matters less than volume. The state of the cancer elsewhere matters most. That finding, more than any machine, made radiosurgery the first choice for brain metastases.
The treatment day
One day for planning. One day, or a few, for treatment.
Is a frame screwed to the head?
| Step | When | Duration |
|---|---|---|
| Consultation and tumor board | Day one | One to two hours |
| Mask, planning CT and thin-slice MRI with contrast | Day one or two | One hour |
| Outlining, planning and physics checks | Two to four days | No visit needed |
| Treatment | Day four to six | Thirty to sixty minutes on the couch |
| Observation and discharge | Same day | A steroid dose, then home |
| Further sessions if planned | Following days | Same routine, shorter |
Risks and follow-up
Fewer than after surgery. Different in kind.
What is radiation necrosis?
- Headache, nausea or tiredness for a day or two, treated with a short course of steroids.
- Temporary hair loss in a small patch where beams enter, in some patients.
- Swelling around the target in the first weeks, which can bring back the symptoms the tumor caused before they improve.
- For targets near a nerve, a small risk of hearing loss, facial numbness or weakness, or visual change, quoted for each patient from the plan.
- MRI at three months. The first check, and in many patients the moment the tumor is seen to have shrunk.
- MRI every three months in the first year for metastases. New deposits are found while still small and treated the same way, at the same visit if the patient lives nearby.
- MRI every six to twelve months for benign tumors. Judged over years.
How soon does it work?
Coming from abroad
Radiosurgery suits travel. The length of stay is five to seven nights for a single session and up to ten for a course of five, the patient walks out of the department after each, and patients are fit to fly the day after the last one. What the team needs before the visit is the MRI as image files with the contrast sequences, the pathology of the primary cancer, the current systemic treatment and any previous radiation to the head with its dose record. The reply, within a few working days and without charge, says whether the target suits radiosurgery, how many sessions are proposed, whether surgery or whole brain radiation would serve better, and the cost.
One coordinator from the international patients office handles arrangements from the first message through discharge and answers the same WhatsApp number once you are back home. The office works in English, Arabic, French, Russian, Serbian, Romanian and Spanish and books interpreters for other languages. It arranges the visa invitation letter, airport transfers, daily transport and accommodation near the hospital, and the follow-up MRI is reviewed by the same oncologist wherever it is done, so that patients do not need to return for the three-month check unless something has changed.
Cost
One figure, after the file review.
It depends on the number of targets, the number of sessions and whether an MRI is repeated at the hospital. Hospitals in this market quote radiosurgery as a package for the course, with the planning MRI and imaging included and accommodation listed separately.
Confirm what it includes. Confirm, too, whether a second session for a new metastasis, should one appear, is priced the same way.
References
- Brown PD, Jaeckle K, Ballman KV, et al. Effect of radiosurgery alone vs radiosurgery with whole brain radiation therapy on cognitive function in patients with 1 to 3 brain metastases. A randomized clinical trial. JAMA. 2016;316(4):401-409.
- Yamamoto M, Serizawa T, Shuto T, et al. Stereotactic radiosurgery for patients with multiple brain metastases (JLGK0901). A multi-institutional prospective observational study. Lancet Oncol. 2014;15(4):387-395.
- Lunsford LD, Niranjan A, Flickinger JC, Maitz A, Kondziolka D. Radiosurgery of vestibular schwannomas. Summary of experience in 829 cases. J Neurosurg. 2005;102 Suppl:195-199.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Prof. Dr. Özcan YILDIZ, Medical Oncology.
Medically reviewed by

Prof. Dr. Özcan YILDIZ
Medical Oncology
Related Treatments
View All
Brachytherapy - Internal Radiation Therapy
A beam from outside has to cross healthy tissue to reach a tumor. Brachytherapy avoids that by placing a rice-sized radioactive source inside the tumor for a few minutes, then taking it out again. It is an essential part of curing cervical cancer and a tested option for womb, prostate and early breast cancer.
Brain Tumor Radiation Therapy
The plan for a brain tumor starts with what must be protected, the optic nerves, the brainstem, the hippocampus, and then shapes the dose around them. Radiosurgery in one to five sessions now treats most metastases, and six weeks of radiotherapy with temozolomide remains the standard after surgery for glioblastoma.
Chemoradiation Therapy - Concurrent Chemoradiotherapy
Blood test on Monday, a drip on Tuesday, radiotherapy every weekday, and the same again for six or seven weeks. Chemoradiation asks more of a patient than either treatment alone and, for several cancers, cures more. See the survival gains trial by trial, the side effects they came with, who is fit for it and how a long stay is organized.
Elekta Versa HD Radiation Therapy
The Elekta Versa HD is the linear accelerator on which Biruni Hospital delivers external beam radiation therapy, with a 160-leaf collimator, high dose rate beams and cone beam CT imaging before every session. This page covers the techniques, from VMAT to radiosurgery, the cancers treated, what large trials show about shorter courses for breast, prostate and metastases, the path from first visit to last session, side effects, and how patients from abroad arrange treatment.
Glioblastoma Radiation Therapy
A glioblastoma has no edge, so surgery alone is never enough. Radiation covers the cavity and a margin of brain around it, together with a daily temozolomide capsule, over six weeks or three depending on age and fitness.