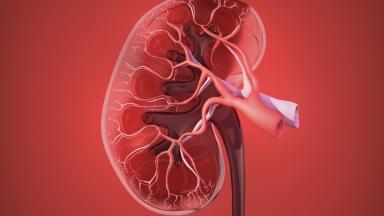
Pediatric kidney transplant replaces a child's failed kidneys with a healthy kidney from a living parent or relative, restoring growth, energy and school life in a way dialysis cannot. Transplant before dialysis gives the best survival. Our pediatric nephrology and transplant team evaluates child and donor, prepares the bladder where needed, performs both operations and follows you once you are back home.
About This Department
Pediatric Transplantation
For a child with kidney failure, a transplant works better than dialysis. Ideally it comes before dialysis starts at all.
Pediatric kidney transplant, or child kidney transplant, replaces a child's failed kidneys with one healthy kidney, for most children from a living parent or relative. The commonest reasons are kidneys and urinary tracts that formed abnormally before birth, followed by nephrotic syndrome, inherited diseases such as cystinosis and polycystic kidney disease, and kidney damage after infections. Transplant restores growth, energy and schooling in a way dialysis cannot. In an Australian and New Zealand registry of 1,634 children followed for four decades, the risk of death on dialysis was more than four times that after transplant (McDonald and Craig, New England Journal of Medicine, 2004). A transplant done before dialysis becomes necessary, called preemptive, gives the best results of all. This page explains the causes, transplant against dialysis, timing and size, the living donor, evaluation of the child including the bladder, the operation, life after transplant, complications, and how families from abroad arrange treatment at Biruni Hospital in Istanbul.
4
Times higher risk of death for children on dialysis than after a kidney transplant, in a 40-year registry
69
Percent higher risk of death for children who had dialysis before transplant than for those transplanted first
3.1
Deaths per 10,000 living kidney donors from the operation, in 80,347 US donors
Free
Review of your child's records by our pediatric nephrology and transplant team
Kidney damage after infection or a complement defect
Atypical forms need special medicine
Glomerulonephritis
Immune inflammation of the kidneys
Transplant after the disease settles
Kidney failure in children develops slowly in most cases, over months or years of chronic kidney disease. Pediatric nephrologists follow the kidney function and plan transplant well before it runs out, so that the family has time to prepare and a donor can be assessed.
Congenital anomalies of the kidney and urinary tract cause about half of kidney failure in children.
Transplant or dialysis
Dialysis keeps a child alive, but it replaces only part of what kidneys do. Hemodialysis means three sessions a week in a unit, and peritoneal dialysis means nightly exchanges at home through a tube in the abdomen. Growth slows, schooling suffers, diet and fluids are strictly limited, and the heart and blood vessels age faster.
1
The burden of dialysis
Children on dialysis miss school, grow poorly despite growth hormone and depend on a machine. Dialysis is a bridge, and transplant is the goal for nearly every child.
Treatment with dialysis was associated with a risk of death more than four times as high as renal transplantation, and increasing the proportion of children treated with transplantation rather than dialysis can improve survival further (McDonald and Craig, 2004).
Dialysis and transplant compared
Aspect
Dialysis
Transplant
Survival
Lower
Higher
Growth and development
Slowed
Improves, especially in younger children
School and daily life
Sessions or nightly treatment
Normal attendance after recovery
Diet and fluids
Strict limits
Few limits
A kidney transplant is not a cure for life. A living donor kidney in a child lasts on average around 15 to 20 years, and most children will need a second transplant in adulthood. Planning for that is part of care from the start.
Transplant before dialysis
Compared with children undergoing preemptive transplantation, children on dialysis for more than 18 months had an 89 percent higher risk of death, regardless of donor source (Amaral and colleagues, Kidney International, 2016).
1
Preemptive transplant
When kidney function falls to about 10 to 15 percent of normal and a living donor is ready, the transplant can take place before dialysis is ever needed. This avoids a dialysis catheter, protects the blood vessels and spares the child months of treatment.
Preemptive transplant needs early referral, while the child is still well. Families who contact a transplant center as soon as their child's kidney function declines steadily have the best chance of avoiding dialysis altogether.
Choosing the right moment
Too early wastes kidney function, and too late costs health.
The team tracks the child's kidney function, growth, blood pressure, anemia and bone health over months, and plans transplant for the point where the remaining kidneys can no longer keep up, ideally before dialysis. That point differs from child to child. Numbers alone do not decide. A child growing well at school with 15 percent function may wait a little, while another with the same number who has stopped growing, feels tired all the time and cannot keep food down is ready now. Donor testing starts months ahead, because it takes time.
Families decide nothing alone. The team walks them through each step.
Age and size
A transplanted kidney is almost always an adult kidney, from a parent or relative. Small children receive an adult kidney too, placed inside the abdomen where there is room, and connected to the large blood vessels. The adult kidney needs a large volume of blood flow, and the anesthetist and surgeon manage fluids carefully during and after the operation.
Transplant at different sizes
Child
Where the kidney is placed
Special points
Under about 10 to 15 kilograms
Inside the abdomen, joined to the aorta and vena cava
Many centers wait until the child reaches this weight, with dialysis if needed
Older children
Lower abdomen, outside the peritoneum, as in adults
Standard technique
Adolescents
As in adults
Attention to taking medicines independently
1
Small children
Babies are usually supported with dialysis until they grow to about 10 kilograms or one to two years of age, when transplant becomes safer. Nutrition through a feeding tube helps them reach that point.
The living donor
Who can be a donor
Criterion
Usual requirement
Note
Age
18 to about 65
Assessed individually
Blood group and crossmatch
Compatible, negative crossmatch
Incompatible transplants possible in selected cases
Health
Normal kidney function, no diabetes, normal blood pressure
Two healthy kidneys needed
Relationship
Family member, with documents
Required by Turkish law for foreign patients
Is it safe for a parent to give a kidney?
Donation is major surgery, done in most centers by keyhole laparoscopic nephrectomy. Serious complications are uncommon and death is very rare. Living with one kidney does not shorten life expectancy in carefully selected donors, though the lifetime risk of kidney disease rises slightly, so donors have yearly checks of blood pressure and kidney function.
Donor recovery
Time
Stage
Activities
Days 1 to 4
Hospital
Walking from the first day
Weeks 2 to 4
Home recovery
Light activity, no heavy lifting
Weeks 4 to 6
Back to normal
Work and most sport
Surgical mortality from live kidney donation was 3.1 per 10,000 donors, and long-term risk of death was no higher for live donors than for matched healthy nondonors (Segev and colleagues, JAMA, 2010).
An independent doctor from outside the child's team confirms that the donor is healthy and giving freely. Donors can withdraw at any stage.
Evaluation of the child
Tests before transplant
Test
Purpose
Note
Blood group, tissue typing, antibodies
Match with the donor
Crossmatch repeated just before surgery
Bladder assessment, urodynamics
Checks the bladder can hold and empty urine
Essential in urinary tract anomalies
Heart and blood vessel scans
Fitness and vessel access
Planned for small children
Infection screening, CMV and EBV
Guides medicines after transplant
Vaccinations completed beforehand
1
The bladder comes first
Many children with congenital urinary tract problems have a bladder that does not store or empty urine properly. A new kidney draining into such a bladder would be damaged. Treatment can include regular catheterization, medicines or bladder surgery before transplant.
2
Vaccinations
Live vaccines such as measles, mumps, rubella and chickenpox must be given before transplant, since they cannot be given afterwards.
The operation
A typical hospital course for the child
Period
Where
Main focus
Days 1 to 3
Pediatric intensive care or transplant unit
Fluids, urine output, blood flow in the kidney
Days 4 to 10
Transplant ward
Medicine levels, catheter and drain removal
Weeks 2 to 6
Nearby accommodation
Clinic visits two to three times a week
The donor and child operations take place on the same day. The donor operation takes two to three hours, the child's three to four. The kidney usually starts making urine at once, and blood tests show falling creatinine within the first days.
1
Early complications
Delayed function, clots in the kidney's vessels, urine leaks and early rejection are watched for with daily blood tests and ultrasound.
A small stent placed in the ureter during surgery protects the join while it heals, and comes out after a few weeks in a short procedure under sedation.
After transplant
Immunosuppressant medicines are taken every day for as long as the kidney works. Missing doses is the commonest preventable cause of losing a transplanted kidney, especially in teenagers.
Most children take tacrolimus with mycophenolate, with or without low-dose steroids. Levels are checked often. Before going home, children and parents learn the name, dose and time of every medicine, and practice giving them under the eye of a transplant nurse until it becomes routine.
Adolescence is the riskiest period for a transplanted kidney. Teenagers take over their own medicines gradually, with support.
Follow-up after transplant
Item
Frequency
Purpose
Blood and urine tests
Weekly at first, then monthly, then every three months
Kidney function, drug levels
Ultrasound
As needed
Blood flow and drainage
Growth and development
Every visit
Height, weight, school progress
Growing up with a new kidney
Growth picks up after transplant.
Younger children gain the most, and some catch up in height, while teenagers gain less because their growth plates close sooner, which is one reason to transplant early. Appetite improves and diet opens up. Children return to school within two to three months and can play most sports, avoiding hard contact over the kidney. Schools are told about infection risks and the need for medicines at set times. The move to an adult transplant clinic happens in the late teens, prepared over several years so that the young person arrives able to manage their own care.
Complications
Complications and their treatment
Complication
When
Treatment
Acute rejection
First months, sometimes later
Steroid pulses or other treatment, usually reversed
Recurrence of FSGS
Days to weeks
Plasma exchange and other treatment
Infections, CMV, EBV, BK virus, urinary infections
Parents learn the warning signs before discharge and have a number to call day and night.
The first year carries the highest risk of complications, and close follow-up during this period protects the kidney.
Warning signs for parents
Sign
Possible cause
What to do
Fever
Infection or rejection
Call the team the same day
Less urine, swelling, rising blood pressure
Rejection or blockage
Call the team
Vomiting and unable to keep medicines down
Risk of low drug levels
Call the team at once
A kidney that fails after years can be followed by a second transplant, from another relative or a deceased donor in the home country.
Good adherence, blood pressure control and prompt treatment of infections are what keep a transplanted kidney working longest.
For families from abroad
Children from abroad receive a kidney from a living relative, since deceased donor organs in Turkey are allocated through the national system. Turkish law requires the relationship between donor and child to be documented before surgery. Send your child's kidney reports, the latest blood tests, ultrasound and any bladder studies, together with the blood groups of possible donors, and our team advises on timing.
1
Length of stay and fitness to fly
Plan about six to eight weeks in Istanbul, one to two weeks for evaluation of child and donor, one to two weeks in hospital and close follow-up afterwards. The donor can fly after about two to three weeks. The child flies once kidney function and medicine levels are stable.
Once you are back home, your pediatric nephrologist continues follow-up with our written plan, blood results are shared with us, and our team remains reachable for questions.
One coordinator from the international patients office handles arrangements from the first message through discharge and answers the same WhatsApp number once you are back home. The office works in English, Arabic, French, Russian, Serbian, Romanian and Spanish and books interpreters for other languages, and it arranges the visa invitation letter, airport transfers, daily transport and accommodation near the hospital. Halal, vegetarian and diabetic meals, a prayer room on site, and a female physician on request wherever the rota allows.
Documents for living donation
Document
Purpose
Note
Family register or birth certificates
Proves the relationship
Apostilled or consular-certified, translated
Passports of child and donor
Identity
Valid for the whole stay
Medical reports
Diagnosis, dialysis history, blood group
Sent before travel
Cost
The quote is a package covering child and donor, based on the child's condition.
What a quote for pediatric kidney transplant covers
Item
Included
Priced separately
Evaluation
Child and donor tests, consultations
Bladder surgery or other preparation
Surgery
Both operations, intensive care, hospital stay
Treatment of complications, stent removal if done later at home
After discharge
Clinic visits and tests during the stay
Medicines after return home, accommodation
Complications that extend the stay add to the cost, and the quote explains how these are handled. Compare packages that include the same items, especially the donor evaluation and the follow-up weeks.
1
Before you compare
Ask whether the package includes evaluation of a second donor if the first is not suitable, and which medicines are provided for the journey home.
References
McDonald SP, Craig JC. Long-term survival of children with end-stage renal disease. N Engl J Med. 2004;350(26):2654-2662.
Amaral S, Sayed BA, Kutner N, Patzer RE. Preemptive kidney transplantation is associated with survival benefits among pediatric patients with end-stage renal disease. Kidney Int. 2016;90(5):1100-1108.
Dharnidharka VR, Fiorina P, Harmon WE. Kidney transplantation in children. N Engl J Med. 2014;371(6):549-558.
Segev DL, Muzaale AD, Caffo BS, et al. Perioperative mortality and long-term survival following live kidney donation. JAMA. 2010;303(10):959-966.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Prof. Dr. Burçak YILMAZ, Nuclear Medicine.