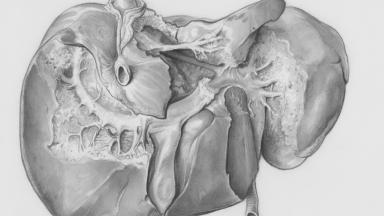
Liver transplant surgery replaces a failing liver, and for international patients in Turkey the usual route is part of a liver from a living relative, which regrows in both donor and recipient within months. We explain who qualifies, the donor's real risks, the legal rules for foreign patients, the operations and the three-month stay.
About This Department
Organ Transplantation
A liver transplant from a living relative can save a life without waiting for a deceased donor. A healthy person accepts a real risk to give it, and that choice must be free.
Liver transplant surgery replaces a failing liver with a healthy one, either a whole liver from a deceased donor or part of a liver from a living donor, whose remaining liver regrows within months. For international patients in Turkey, a living donor from the family is the usual route. In a study of 807 American patients with a potential living donor, those who received a living donor transplant had a 44 percent lower risk of death than those who waited. For the donor, a worldwide survey of 11,553 operations found a death rate of 0.2 percent, and a detailed American study found complications in 40 percent, most of them minor.
44% lower
Risk of death with a living donor transplant against waiting, Gastroenterology 2007
0.2%
Donor deaths in 11,553 living liver donations worldwide, Liver Transpl 2013
85%
Alive at 4 years after transplant for liver cancer within the Milan criteria, NEJM 1996
Free
Transplant team review of your reports
Free consultation
Send the patient's recent blood tests including bilirubin, INR, creatinine and albumin, a CT or MRI of the liver, the diagnosis and treatment history, and the blood group. Tell us who in the family is willing to be assessed as a donor, with their age, blood group and relationship. The transplant team replies with whether transplantation fits, how soon it is needed, and what the legal and medical steps would be. The review is free and commits neither patient nor donor to anything.
Families who search for liver transplant surgery are usually facing two decisions at once, one for the patient and one for the relative who might donate. This page treats both with equal care. It covers who needs a transplant, how living donation works, the donor's risks in plain numbers, the legal rules for international patients, the operations, the medicines that follow for life, and how long the family must plan to stay.
Who needs a liver transplant
Doctors consider a transplant when the liver can no longer keep the patient alive, or soon will not.
When the liver fails
The common reasons
Cirrhosis from hepatitis B or C, alcohol or fatty liver disease, once it causes fluid in the abdomen, bleeding from swollen veins, confusion, jaundice or kidney failure. Liver cancer within agreed size limits in a cirrhotic liver. Sudden liver failure from a virus, a drug or a poison. Rarer diseases too, such as primary sclerosing cholangitis and autoimmune liver disease, and in children biliary atresia and inherited metabolic disorders that the liver cannot correct on its own. Doctors use the MELD score, calculated from bilirubin, INR, creatinine and sodium, to rank how soon a transplant is needed.
Living donor transplantation
Part of a healthy liver, taken from a living person, can replace a whole failing one.
How it works
1
The donor gives part of the liver
For an adult recipient, usually the right lobe, about 55 to 65 percent of the liver. For a child, a small left lateral segment.
2
The recipient receives it
The failing liver is removed and the graft is connected to the recipient's vessels and bile duct.
3
Both livers regrow
The donor's remaining liver and the graft both grow toward full size within about three months.
Why the liver can regrow
Liver cells divide again when part of the organ is removed. No other solid organ does this to the same degree. The donor keeps enough liver to live normally from the first day, as long as the remnant is at least about 30 percent of the original.
Why it matters
Receiving a living donor liver lowered the risk of death by 44 percent
An American study followed 807 patients who had a potential living donor evaluated. Compared with those who waited for a deceased donor or stayed on the list, those who received a living donor liver had an adjusted hazard ratio for death of 0.56. At centers with more than 20 such operations, the ratio fell to 0.35. The authors stressed that this benefit must be weighed against the donor's risk. Berg and colleagues, Gastroenterology, 2007.
Who can donate
1
The right relationship
A relative or spouse, with legal proof.
2
A compatible blood group
Donor and recipient blood groups must match or be compatible, in the same way as for a blood transfusion.
3
Good health
Adults typically 18 to 55, of healthy weight, without significant fatty liver, and with a liver large enough to share.
The donor's risk, told plainly
A donor gains nothing medically from the operation.
Donation is voluntary, and a donor may withdraw at any stage, even on the morning of surgery, with the team giving a medical reason to the family.
An independent doctor, outside the recipient's team, speaks for the donor and can stop the process.
The donor goes through the full evaluation, and the team may turn a donor down for the donor's own protection even when the recipient's need is great, a decision that is final and is explained to the family without disclosing the donor's private medical details.
The donor's own follow-up continues for at least a year after surgery.
A worldwide survey
Seventy-one programs in 21 countries reported on 11,553 living liver donations. Complications occurred in 24 percent. Twenty-three donors died, 0.2 percent, most within 60 days, and five needed a liver transplant themselves. A near-miss, a life-threatening event without lasting harm, occurred in 1.1 percent, more often at programs with 50 or fewer donations. Cheah and colleagues, Liver Transplantation, 2013.
A detailed American cohort
Among 740 completed donations, 40 percent of donors had at least one complication, mostly minor. Three donors died. Hernias appeared in 7 percent and psychological difficulties in 3 percent more than a year later. Ninety-five percent of complications resolved within a year, but only 75 percent of hernias and 42 percent of psychological problems did. Abecassis and colleagues, American Journal of Transplantation, 2012.
What donors describe afterward
Pain for one to two weeks, tiredness for one to three months, return to office work in six to eight weeks and to heavy physical work in about three months. A long scar. Most say they would donate again.
The legal rules and the evaluation
Close regulation surrounds living donation. The paperwork forms part of the medical process, and missing documents are the commonest reason a family's trip is delayed.
The law
Related donors and the ethics committee
Turkish law allows living donation from relatives and spouses, and from other donors only with the approval of an ethics committee that checks there is no payment or pressure. International patients bring their donor, together with documents proving the relationship and identity, officially translated and certified in their home country. Organs from deceased donors are allocated through the national system, and international patients should plan on a living donor. Organ buying is a crime. Refuse any offer.
The evaluation
For patient and donor
1
Documents
Relationship and identity documents are reviewed before travel, to avoid a wasted trip.
2
Recipient tests
Blood tests, heart and lung checks, a CT of the liver and vessels, and screening for infection and cancer.
3
Donor tests
Blood tests, a CT or MRI that measures the liver volume and maps its vessels and bile ducts, a heart check, and in some cases a liver biopsy for fat.
4
Psychological assessment and consent
Separate interviews with donor and recipient, and time to reflect before signing.
Two to three weeks in most cases
The evaluation of both is completed in Istanbul in about two to three weeks when the reports sent in advance are complete. In sudden liver failure the process is compressed into days.
The operations
Two operations, one day.
1
The donor operation
Four to six hours under general anesthesia. The surgeon removes the chosen part of the liver through an abdominal incision, or through smaller incisions in selected centers.
2
The recipient operation
Eight to twelve hours. The failing liver is removed and the graft's veins, artery and bile duct are joined to the recipient's.
3
Intensive care
The recipient spends one to five days in intensive care, the donor usually one night in high-dependency care.
How the operations run together
The two operations take place in neighboring theaters on the same day. The donor operation starts first, and the recipient's diseased liver is removed only once the graft is confirmed suitable, so that no one is harmed if the plan must stop.
Transplantation for liver cancer
For some liver cancers, a transplant removes both the cancer and the cirrhotic liver that caused it.
The Milan criteria
Who qualifies
One tumor up to 5 centimeters, or up to three tumors each up to 3 centimeters, with no invasion of the large vessels and no spread outside the liver. Many centers now accept somewhat larger tumors under extended criteria, especially with a living donor, after careful discussion of the higher risk of recurrence.
The results
The original Milan study
75 percent alive at four years, 85 percent within the criteria
In 48 patients with cirrhosis and small liver cancers, survival at four years was 75 percent overall and cancer returned in 8 percent. In the 35 whose tumors were within the criteria on final pathology, survival was 85 percent, against 50 percent in those whose tumors exceeded them. Mazzaferro and colleagues, New England Journal of Medicine, 1996.
Life after transplant
The new liver needs lifelong protection from the immune system, and the patient carries most of that responsibility.
Anti-rejection medicines
Every day, for life
Tacrolimus is the main drug for most patients, with mycophenolate and steroids in the first months. Blood levels are measured often at first, then every few months. Missing doses is the commonest cause of late rejection.
Their side effects
Higher risk of infection, raised blood pressure and blood sugar, kidney strain, tremor and a higher long-term risk of skin cancer. The doses are kept as low as safely possible, and regular checks catch problems early.
Complications in the first months
What the team watches for
Rejection, found by blood tests and confirmed by biopsy, and treated with extra medicine. Narrowing or leakage of the bile duct, treated by endoscopy. Clotting of the hepatic artery, which is rare but serious. Infections, especially in the first three months. Return of the original disease, such as hepatitis B, which is prevented with antiviral tablets.
Length of stay and flying
The recipient's stay is the longest part of the journey. Three months away from home asks a lot of a family, and planning for it early, with a companion who can stay throughout, work arrangements and accommodation close to the hospital, makes the recovery calmer and safer. Donors return home much sooner.
Plan on about three months for the recipient
Recipients stay in hospital two to four weeks, then live near the hospital for close follow-up, with blood tests two or three times a week, until about three months after surgery. Donors are discharged in about a week and can fly home two to four weeks after surgery, once the surgeon has checked the wound.
This table scrolls sideways on a narrow screen. Swipe or drag to see every column.
A typical timeline
Stage
Recipient
Donor
Evaluation
Two to three weeks
Two to three weeks, in parallel
Hospital stay after surgery
Two to four weeks
Five to ten days
Nearby stay for follow-up
Until about three months
Until the first wound check
Flying home
After about three months, with the team's approval
Two to four weeks after surgery
Flying after transplant is safe once the team agrees. Carry all anti-rejection medicines in hand luggage with a letter from the team, and take enough for delays. Avoid crowds and people with infections during the first months.
Cost and arrangements
Quotes follow the evaluation.
1
What decides the cost
Whether the transplant is from a living donor, the length of intensive care and hospital stay, the donor's evaluation and surgery, and the first months of medicines. Published packages in Istanbul cover the evaluation of both, both operations, the hospital stay within stated limits, an interpreter and transfers, and leave out accommodation during the follow-up months and flights. The team's review of the reports is free, and a written estimate follows the evaluation.
2
What the office arranges
The coordinator writes in English, Arabic, French, Russian, Serbian, Romanian or Spanish, or arranges an interpreter, checks the legal documents before travel, sends an appointment confirmation and invitation letters naming the hospital and the treating doctor for patient, donor and a companion, and helps find accommodation near the hospital for the months of follow-up. Halal, vegetarian and diabetic meals are available, a prayer room is on site, and you may request a female doctor at first contact.
Follow-up at home
The transplant does not end at the airport. Once you are back home, doctors near you carry the care for life, and the transplant team stays part of it.
A lifelong partnership
With your doctors at home
A hepatologist at home takes over after three months
Once you are back home, a liver specialist there follows the written plan, with blood tests and drug levels at set intervals, yearly scans and skin checks. The transplant team remains available to review results, and the coordinator stays reachable on the same WhatsApp number. Fever, jaundice, dark urine, pale stools or abdominal pain after transplant need a doctor the same day.
Liver Transplant Surgery FAQ
Can a foreigner have a liver transplant in Turkey?
Yes, from a living donor. International patients bring a related donor, or a spouse, with documents proving the relationship. Other donors need ethics committee approval. Organs from deceased donors are allocated through the national system.
Is living liver donation safe for the donor?
It carries a real risk. A worldwide survey of 11,553 donations found a death rate of 0.2 percent and complications in 24 percent, and a detailed American study found complications, mostly minor, in 40 percent. Donors should decide freely and may withdraw at any time.
How long does the donor's liver take to regrow?
Both the donor's remaining liver and the graft grow toward full size within about three months.
What are the survival rates after liver transplant?
They depend on the disease and the patient's condition. In an American study, a living donor transplant lowered the risk of death by 44 percent compared with waiting. For liver cancer within the Milan criteria, 85 percent were alive at four years in the original study.
How long do we need to stay in Turkey?
About three months for the recipient, including two to three weeks of evaluation, the hospital stay and close follow-up. The donor can usually fly home two to four weeks after surgery.
Will I need medicines for life?
Yes. Anti-rejection medicines are taken every day for life, at the lowest dose that protects the liver, with regular blood tests.
References
Berg CL, Gillespie BW, Merion RM, et al. Improvement in survival associated with adult-to-adult living donor liver transplantation. Gastroenterology. 2007;133(6):1806-13.
Cheah YL, Simpson MA, Pomposelli JJ, Pomfret EA. Incidence of death and potentially life-threatening near-miss events in living donor hepatic lobectomy, a world-wide survey. Liver Transpl. 2013;19(5):499-506.
Abecassis MM, Fisher RA, Olthoff KM, et al. Complications of living donor hepatic lobectomy, a comprehensive report. Am J Transplant. 2012;12(5):1208-17.
Mazzaferro V, Regalia E, Doci R, et al. Liver transplantation for the treatment of small hepatocellular carcinomas in patients with cirrhosis. N Engl J Med. 1996;334(11):693-9.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Gökhan Özgür, Internal Medicine (Hematology).