Tumor ablation destroys a small tumor in place with heat, cold or alcohol through a probe placed under ultrasound or CT guidance, without an incision and with one night in hospital at most. It covers radiofrequency, microwave and cryoablation, the liver, kidney, lung, bone and thyroid tumors treated, how ablation compares with surgery and radiation, what the randomized trials show, the day of the procedure, the risks and follow-up, and how patients from abroad arrange it in Istanbul.
About This Department
Interventional oncology
A needle through the skin, guided by ultrasound or CT, heats or freezes a tumor until it dies. No incision, no organ removed, home the next day. For the right tumor, it matches surgery.
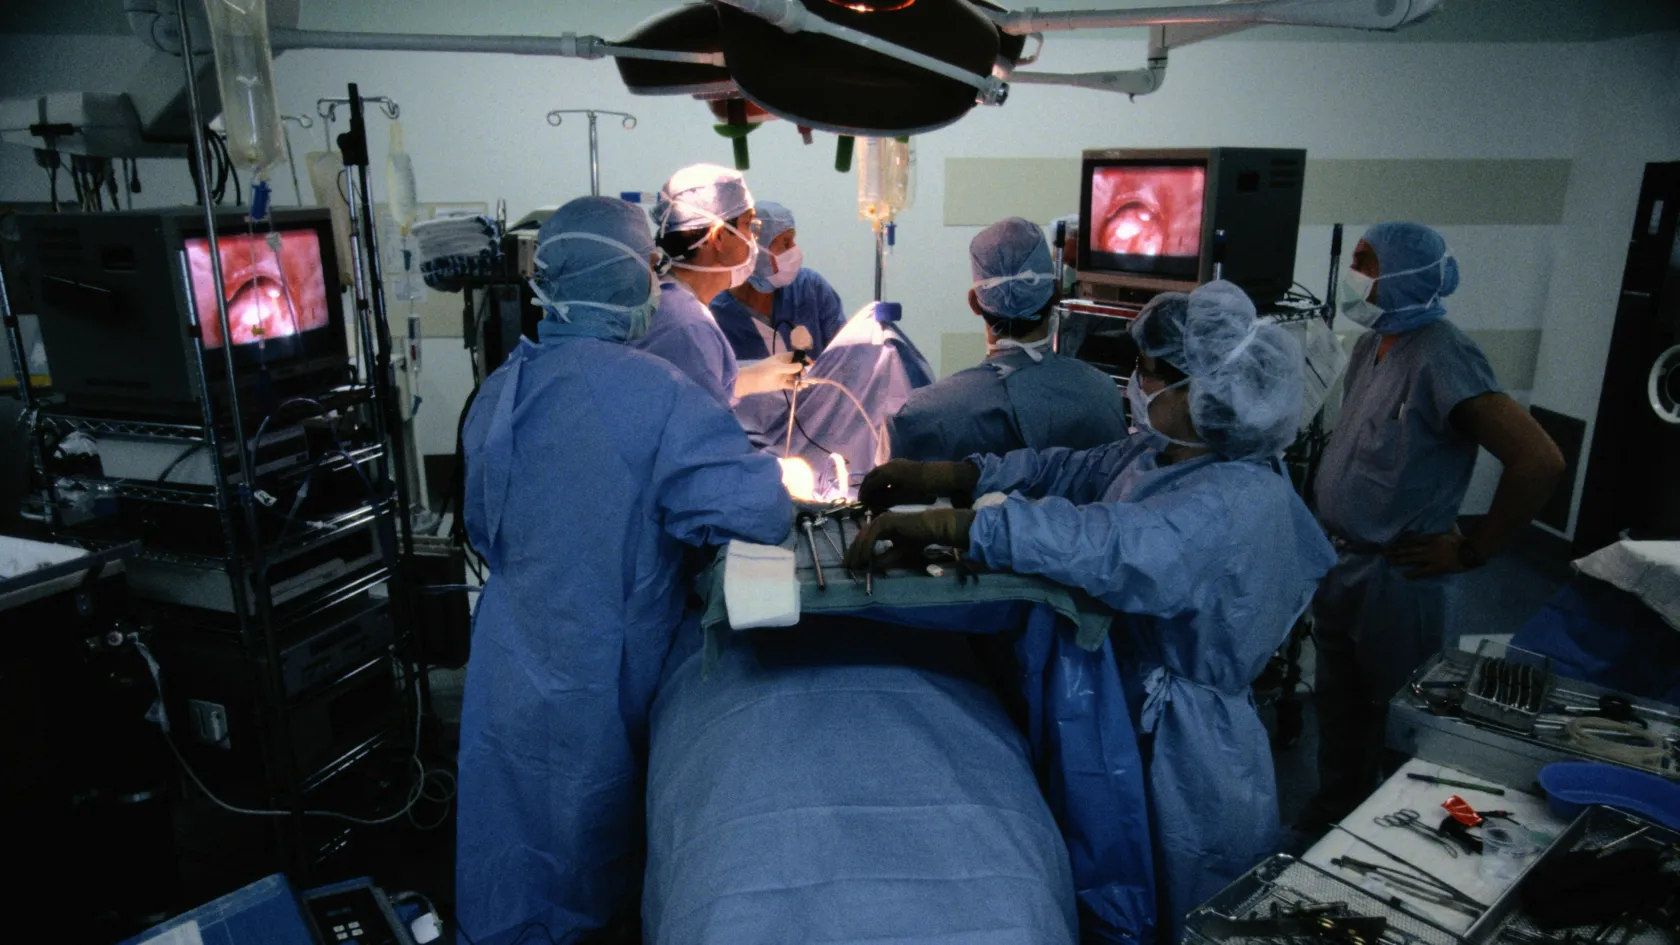
Tumor ablation destroys a tumor in place, with heat from radiofrequency or microwave energy, with cold, or with alcohol, delivered through a probe placed under imaging guidance. It is called tumor destruction surgery in some countries, though no surgery in the ordinary sense takes place. A randomized trial of 180 patients with a single liver cancer of five centimeters or less found survival at three years of 71.4 percent after ablation and 73.4 percent after surgical removal, with fewer and milder complications after ablation (Chen and colleagues, Annals of Surgery, 2006). A European trial then showed that adding ablation to chemotherapy for colorectal cancer that had spread to the liver raised survival at eight years from 8.9 to 35.9 percent (Ruers and colleagues, Journal of the National Cancer Institute, 2017). This page explains how ablation works and which methods exist, which tumors it treats, how it compares with surgery and radiation, what the trials show, what the day involves, the risks and the follow-up, and how patients from abroad arrange it at Biruni Hospital in Istanbul.
71.4
Percent alive at three years after ablation of a small liver cancer, against 73.4 percent after surgery, in the randomized trial
35.9
Percent alive at eight years when ablation was added to chemotherapy for colorectal liver metastases, against 8.9 percent
96
Percent cancer-specific survival at five years after radiofrequency ablation of a small kidney tumor, against 99 percent after partial nephrectomy
Free
Review of your CT or MRI and the tumor board's recommendation
Cancer cells die above 60 degrees Celsius within seconds and below minus 40 within minutes. Ablation delivers one or the other to a volume of tissue a little larger than the tumor, through a probe the width of a pencil lead. The dead tissue stays. The body absorbs it over months. The probe reaches the tumor through the skin in most cases, guided by ultrasound or CT, and the procedure takes thirty to ninety minutes.
The methods
Method
How it works
Where it fits
Radiofrequency ablation, RFA
An electrical current heats the tissue around the probe tip to 60 to 100 degrees
Liver, kidney, lung, bone and thyroid tumors up to 3 centimeters, the longest track record
Microwave ablation, MWA
Microwaves heat a larger volume faster and are less affected by nearby blood vessels
Liver and lung tumors up to 4 to 5 centimeters, now the commonest choice
Cryoablation
Argon gas freezes the tissue to minus 40 and below in cycles, with the ice ball visible on CT
Kidney, bone, lung, breast and soft tissue tumors, and tumors near nerves, where the visible ice ball protects them
Ethanol injection
Alcohol injected into the tumor dehydrates and kills it
Small liver cancers in a cirrhotic liver where a heat probe is unsafe, and thyroid cysts
Irreversible electroporation, IRE
Electrical pulses open the cell membranes without heat
Tumors wrapped around vessels or bile ducts that heat would damage, in specialist centers
1
Through the skin
The route for nine procedures in ten. Local anesthetic and sedation, or a short general anesthetic, and a probe placed under ultrasound or CT.
2
Laparoscopic
Through small incisions with a camera, when the tumor sits on the surface of the liver next to the bowel or the diaphragm and needs to be lifted away, or when several tumors are treated at once.
3
Open, during surgery
The surgeon removes what can be removed and ablates what cannot, in the same operation, which is the combination the colorectal trial below tested.
Which tumors it treats
Small, few and reachable.
1
Liver cancer, hepatocellular carcinoma
A single tumor of three centimeters or less, or up to three tumors each under three centimeters, in a patient with cirrhosis for whom surgery would remove liver that cannot be spared. The commonest use worldwide, and the one with randomized evidence.
2
Liver metastases
Deposits from bowel, breast, neuroendocrine and other cancers, fewer than ten, none over three to four centimeters, with the primary controlled, treated alone or combined with surgery to clear the liver.
3
Kidney
Tumors of four centimeters or less, especially in older patients, patients with one kidney, and those with a genetic tendency to multiple tumors, where preserving kidney tissue matters most.
Complications were more often and severe after surgery than after ablation, and the one-, two-, three- and four-year survival rates after ablation and surgery were 95.8, 82.1, 71.4 and 67.9 percent and 93.3, 82.3, 73.4 and 64.0 percent, with no statistical difference (Chen and colleagues, 2006).
Other sites
Site
Typical use
Notes
Lung
Metastases and early lung cancer in patients unfit for surgery
Competes with stereotactic radiation, which treats larger and central tumors
Bone
Painful metastases, osteoid osteoma, small tumors of the spine and pelvis
Pain relief within days, sometimes combined with cement injection
Thyroid
Benign nodules that cause pressure or cosmetic concern, and selected small cancers
Radiofrequency, under ultrasound, as an alternative to removing the gland
Adrenal
Small functioning tumors and metastases
After blood tests exclude pheochromocytoma
Breast, soft tissue, pancreas
Selected cases in specialist centers
Cryoablation for breast, IRE for pancreas, outside routine practice
1
The size rule
A heat probe destroys a sphere of three to four centimeters, and the plan must cover the tumor plus a margin of five to ten millimeters on every side. A tumor of three centimeters is therefore the comfortable limit for a single probe, four to five for microwave or several probes, and beyond that the chance of leaving live tumor at the edge rises steeply.
2
What ablation does not treat
Tumors against the main bile ducts or the bowel, where heat would injure them. Tumors that cannot be seen on the guiding image. Widespread disease, where destroying one deposit changes nothing. And any tumor that surgery would cure more reliably in a patient fit for it, unless the patient chooses otherwise with the numbers in front of them.
Ablation, surgery or radiation
Three ways to kill a small tumor in place. The tumor board weighs the organ, the size, the position and the patient.
Is ablation as good as surgery?
For a single liver cancer under three centimeters, the randomized trial found equal survival with fewer complications, and guidelines in Europe, America and Asia now treat ablation and resection as alternatives at that size. Between three and five centimeters, surgery clears the tumor more reliably and ablation keeps its place for patients whose liver or general health rules surgery out. For kidney tumors under four centimeters, a series of 1,422 patients found five-year cancer-specific survival of 99 percent after partial nephrectomy, 96 percent after radiofrequency ablation and 100 percent after cryoablation, with no significant difference in recurrence or death (Andrews and colleagues, European Urology, 2019). For lung tumors, stereotactic radiation has largely replaced ablation except where radiation has already been given.
For cT1a patients, clinically relevant differences between partial nephrectomy and ablation are unlikely, and treatment choice should involve shared decision making (Andrews and colleagues, 2019).
What the trials show
One randomized trial against surgery. One randomized trial of ablation added to drugs. One large comparison in the kidney.
Ablation added to chemotherapy
The European trial randomized 119 patients with colorectal cancer that had spread to the liver, fewer than ten deposits, none removable by surgery alone, to chemotherapy or to chemotherapy plus ablation of every deposit, with resection where possible. At a median follow-up of 9.7 years, 65 percent of the combined group had died against 90 percent of the chemotherapy group. Survival at eight years was 35.9 percent against 8.9 percent. The authors called it the first randomized study to show that aggressive local treatment prolongs survival in unresectable colorectal liver metastases (Ruers and colleagues, 2017).
A small liver cancer, ablated rather than cut out, gives the same survival with a shorter stay and fewer complications.
A liver full of metastases that cannot all be removed can still be cleared by combining removal and ablation, and clearing it changes survival at eight years fourfold.
A small kidney tumor can be ablated with the same cancer control as surgery in patients who would rather keep more kidney or avoid an operation.
The day of the procedure
Outpatient or one night. Sore for a few days.
Fasting from midnight. Blood tests for clotting, platelets, kidney and liver function within the previous week. Blood thinners paused on the schedule agreed at booking.
A contrast CT or MRI within a month of the procedure, so that the plan matches what is there now rather than what was there when the diagnosis was made.
A companion to take the patient home, and no driving for 24 hours after sedation.
Will I be asleep?
It depends on the organ and the method. Liver and kidney ablation through the skin is done under deep sedation with an anesthesiologist present, so that the patient feels nothing and breathes steadily on request. Bone and lung ablation, and any procedure that will take more than an hour or use several probes, is done under general anesthesia. Cryoablation hurts less than heat and is sometimes done under local anesthetic and light sedation. The choice is made at the consultation and written on the consent form.
The day
Step
What happens
How long
Arrival
Consent, cannula, sedation or anesthesia
One hour
Placement
Probe advanced under ultrasound or CT, position confirmed on imaging from two angles
Fifteen to thirty minutes
Ablation
Heat applied for five to fifteen minutes per position, or freeze-thaw cycles over twenty to thirty minutes
Twenty to sixty minutes
Check
Contrast CT or ultrasound on the table to confirm the ablation zone covers the tumor with a margin, and a second application if it does not
Ten minutes
Recovery
Observation, pain relief, fluids, a first meal
Four hours to overnight
Home
With painkillers and written instructions, wound check by phone or in person at one week
Next morning for most
Risks and follow-up
Fewer than after surgery. Mostly minor. The serious ones depend on what lies next to the tumor.
Complications
Complication
How often
Notes
Pain and low fever for a few days
Common
The post-ablation syndrome, from the dead tissue, treated with simple painkillers
Bleeding
1 to 2 percent
Higher in cirrhosis and on blood thinners, rarely needs transfusion
Injury to bowel, bile duct, ureter or diaphragm
Under 1 percent
Avoided by fluid injection to push the organ away, or a laparoscopic route
Abscess in the ablation zone
1 to 2 percent
More likely after previous bile duct surgery, treated with drainage and antibiotics
Air leak after lung ablation
20 to 30 percent
Most settle, some need a chest tube
Tumor seeding along the track
Under 1 percent
Prevented by heating the track as the probe is withdrawn
Death
Under 0.5 percent
Reported in large series, almost always in patients with severe liver disease
One month. Contrast CT or MRI. A complete ablation shows a zone larger than the original tumor with no enhancement at its edge. A rim of live tumor is treated again at once.
Every three months in the first year. Imaging and, for liver cancer, the alpha-fetoprotein level. Recurrence at the edge occurs in 5 to 15 percent and is ablated again.
Every six months from the second year. New tumors elsewhere in the same organ are the commoner event in cirrhosis and are treated the same way, which is one of ablation's advantages, since it can be repeated as often as needed.
The ablation zone does not vanish. It shrinks slowly over one to two years and remains visible as a scar on every scan thereafter. A radiologist reading follow-up images needs the earlier ones for comparison, which is why patients from abroad take the disk home.
Coming from abroad
Ablation suits travel.
The whole episode fits in a week, the patient walks out the next morning, and the follow-up is imaging that can be done at home and reviewed here. The length of stay is five to seven nights, which covers the consultation, the tumor board, the scan if a recent one is not available, the procedure, one night in hospital and two days of rest before the flight. Patients are fit to fly on the third day after a liver or kidney ablation and on the fifth after a lung ablation once a chest X-ray is clear. What the team needs before travel is the CT or MRI as image files, the pathology if a biopsy has been done, the liver and kidney function tests, the list of medicines with blood thinners marked, and the record of any earlier treatment to the same organ. The tumor board reviews the file without charge and replies with a recommendation, which is sometimes surgery or radiation rather than ablation, and with the method, the anesthesia, the stay and a cost estimate.
One coordinator from the international patients office handles arrangements from the first message through discharge and answers the same WhatsApp number once you are back home. The office works in English, Arabic, French, Russian, Serbian, Romanian and Spanish and books interpreters for other languages, and it arranges the visa invitation letter, airport transfers, daily transport and accommodation near the hospital. Halal, vegetarian and diabetic meals, a prayer room, a female physician on request wherever the rota allows. The one-month scan is reviewed by the same team wherever it is taken. A return visit is needed only if something has to be treated.
Cost
One figure, after the file review.
Organ, method, number of tumors, anesthesia and the night in hospital set it. Hospitals in this market quote ablation as a package for the procedure, with the probe, the imaging on the table and the overnight stay included and the pre-procedure scan and the follow-up imaging priced separately, which means a patient who arrives with a scan from the last month and has the follow-up done at home pays for the procedure and little else.
Two questions to confirm. What the figure includes. What a second session for a rim of residual tumor would cost.
References
Chen MS, Li JQ, Zheng Y, et al. A prospective randomized trial comparing percutaneous local ablative therapy and partial hepatectomy for small hepatocellular carcinoma. Ann Surg. 2006;243(3):321-328.
Ruers T, Van Coevorden F, Punt CJA, et al. Local treatment of unresectable colorectal liver metastases. Results of a randomized phase II trial. J Natl Cancer Inst. 2017;109(9):djx015.
Andrews JR, Atwell T, Schmit G, et al. Oncologic outcomes following partial nephrectomy and percutaneous ablation for cT1 renal masses. Eur Urol. 2019;76(2):244-251.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Rasim Çırpın, Interventional Radiology / Radiology.