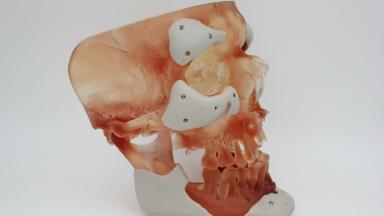
A fracture that has not healed after a year, healed crooked or became infected can still be repaired, and the treatment often runs for months in an external frame. This page explains nonunion, malunion and bone loss repair, the choice between bone transport and the Masquelet technique, and how a long treatment fits around travel to Istanbul.
About This Department
Orthopedics
A fracture that never healed is a problem with a known set of answers. Most of them end with a leg you can walk on.
Complex trauma reconstruction repairs what an injury left behind once the first treatment is over, meaning bone that has not joined, bone that healed crooked or short, a fracture that became infected, and segments of bone or skin that were lost. Across 89 studies and 3,543 adults, bone transport in an external frame rebuilt tibial defects averaging 7 centimeters with a failure rate of 0.9 percent. This page explains how each problem is repaired, what living with a frame involves, how the stay in Istanbul is planned around a treatment that runs for months, and which records to send for a free review.
97%
Tibial nonunions healed with a fine wire frame
94%
Infected fractures with bone loss cured by the end of treatment
0.9%
Failure rate of tibial bone transport, 3,543 adults
Free
Free consultation on your X-rays and CT before you book
The patients who look abroad for this surgery were nearly all injured months or years ago.
In the days after a road accident, a fall or a blast, a first operation saved the limb and held the bone, and now something has gone wrong with the result. Reconstruction deals with that second phase.
Nonunion, a bone that has not joined six to nine months after the injury
Malunion, a bone that joined bent, twisted or shortened
Fracture-related infection, settled in the bone and the metal, with a wound that keeps draining
Segmental bone loss, where a piece of bone was lost in the injury or removed later
Skin and muscle that never closed properly over the shin
Many patients carry two or three of these problems in the same leg, along with a knee or ankle that has stiffened during the long months of treatment, and the plan has to solve them in the right order.
Infection comes first, bone second, alignment and length third.
Bone that has not healed
A nonunion has a reason. The bone may have moved too much under a plate or nail that was not stiff enough, lost its blood supply in the injury, been starved of healing by smoking or diabetes, or harbored a low-grade infection that nobody has yet cultured. Surgeons look for that reason before choosing the repair, because a nonunion fixed again without addressing the cause tends to fail a second time. For the shin bone, the most common site, a systematic review of 26 studies on aseptic diaphyseal tibial nonunions reported union in 88 percent after exchanging the nail for a larger one, 95 percent after a first nail placed across a nonunion that had been treated without one, and 97 percent with a fine wire circular frame. Bone graft from the patient's own pelvis, a cut through the fibula so the tibia can compress, and loosening the nail's locking screws to let the bone ends press together were the usual additions.
At least 88 in every 100 healed.
Infection after a fracture
An infected fracture rarely clears with antibiotics alone, because the bacteria live in a film on the metal and in dead bone that has no blood supply for the drugs to reach. Treatment removes the old implants and every piece of dead bone, takes five or more tissue samples for culture, fills the space with antibiotic-loaded cement or beads, and stabilizes the bone again, in many cases with an external frame. A muscle or skin flap then closes the wound with living tissue. The flap comes from a calf muscle next to the wound, or travels from the thigh or the back as a free flap joined to new blood vessels under the microscope. Across 50 studies and 1,530 patients with infected fractures and large bone defects, infection was cured in 83 percent after the first planned treatment and in 94 percent by the end of follow-up, with recurrence in 8 percent and amputation in 3 percent.
Antibiotics afterward
Antibiotics continue for weeks after the operation.
Nine randomized trials covering 1,723 patients with bone and joint infection found oral antibiotics matched intravenous ones for treatment failure, which lets many patients finish the course at home once the culture result and the regimen are settled.
Rebuilding missing bone
Gaps of a few millimeters fill with bone graft. Larger segmental defects, several centimeters of missing bone, need one of three established methods.
This table scrolls sideways on a narrow screen. Swipe or drag to see every column.
Three ways to rebuild a segmental bone defect
Method
How it works
Published results
Bone transport in a frame
A cut segment of healthy bone is moved across the gap one millimeter a day, and new bone forms behind it
Union 94.6% and infection cleared in 93.0% in infected tibial nonunions
Induced membrane, Masquelet
A cement spacer grows a membrane around itself, then is replaced with bone graft six to ten weeks later
Union 88.0% and infection cleared in 80.4% in the same comparison
Vascularized fibula
The patient's own fibula, moved with its artery and vein and joined to vessels at the defect
Used for long gaps and for the arm, by a microsurgical team
Across 32 studies and 1,136 patients, the differences between transport and the induced membrane fell short of statistical significance, and the choice therefore turns on the gap length, the state of the skin, the joints nearby and how long the patient can live with a frame.
Living with a frame
The frame stays for months.
1
Fitting
The frame goes on under anesthesia, and the surgeon makes a controlled cut through healthy bone away from the defect.
2
Lengthening
A week later the patient or a family member starts turning the frame with a small key, a quarter of a millimeter four times a day.
3
Hardening
New bone forms in the gap and hardens, at a healing index of 54.2 days for every centimeter rebuilt in the 2026 review, and 95 percent of patients bore weight on the leg early.
4
Removal
A short operation takes the frame off, after a mean of 11 months for tibial bone transport.
Pin sites, the points where wires and pins pass through the skin, are cleaned on a set schedule to keep them from becoming infected, and showering with the frame is allowed once the wounds have sealed. Pin site infection, stiffness in the knee or ankle and pain during lengthening are frequent and treated as they come, which explains why the same review called the method demanding and reliable in one sentence. Wide trousers with a side zip go over the frame, a pillow under the calf helps at night, and the discharge letter explains the metal to airport security. Desk work resumes within weeks. Physical work waits for the frame to come off.
Crooked, short or rotated bones
A malunion overloads the joint next to it. The knee, ankle or hip then wears out early. Standing X-rays of both legs measure the angle and the shortening, and a CT scan measures rotation, which X-rays miss. The surgeon then cuts the bone, an osteotomy, and sets it straight.
Small corrections happen in one step with a plate or a nail. Large or combined corrections happen gradually in a computer-planned hexapod frame, adjusted a little each day. Lengthening restores shortening of two to five centimeters, in a frame or with a lengthening nail inside the bone that a magnet outside the leg turns a fraction of a millimeter at a time.
When saving the limb is the harder road
Not every limb should be saved.
Across 47 studies and 8,742 patients with the most severe lower leg injuries, a 2026 meta-analysis found quality of life and function two years later comparable after limb salvage and after amputation.
Salvage brought slightly better return to work, but 4.7 months more recovery, two and a half times the infection rate and 87 percent more readmissions, and 22.7 percent of salvage attempts ended in a later amputation. A patient who has already been through years of failed operations deserves to hear that comparison plainly.
A review of your own records shows which way the evidence points in your case.
Stays, flights and follow-up
Length of stay follows the method. A nail exchange or plate with bone graft needs a week in hospital and the wound check at two weeks before the flight, while a frame keeps the patient in Istanbul until lengthening has started, the first X-ray shows new bone forming, and the patient or a family member can turn the frame and clean the pins without help, two to three weeks in most plans. Infected cases add the time to read the cultures and set the antibiotic plan. The patient room has a companion bed for the whole admission, and that companion is the person who learns the frame care.
Back home
After the flight, X-rays every two to four weeks during lengthening, then every six to eight weeks, go by WhatsApp to the same coordinator, and the surgeon adjusts the plan from them, so care carries on once you are back home.
Frame removal takes a short return visit.
Your coordinator, assigned from the first message, stays with you through every stage, and the international patients team works in English, Arabic, French, Russian, Serbian, Romanian and Spanish, with interpreting in other languages arranged on request. A request for a female surgeon goes to the department and is met wherever the rota allows, and halal, vegetarian and diabetic meals come from the hospital kitchen, a prayer room is on site, the office arranges hotel nights, airport transfers and transport to each appointment, and the invitation letter for the visa goes out ten days before travel.
Call the same day for any of these.
Redness, pus or new pain around a pin
Fever or chills
A wire or pin that feels loose, or a frame that has shifted
Numbness, or a foot that turns cold or pale
What shapes the quote
Most of the cost comes from the number of operations.
An infected nonunion with a bone gap may need a cleaning operation, a spacer or frame, a flap from a plastic surgeon and a later grafting or docking procedure, while an aseptic nonunion may need one, and the frame or nail system, microsurgery for a flap or a vascularized fibula, laboratory cultures, the length of intravenous antibiotics, intensive care and the number of physiotherapy sessions all move the total, and so do diabetes, smoking and earlier failed surgery.
Questions for any offer are how many operations the figure assumes, whether the frame, the flap and the cultures are inside it, what happens if the culture changes the plan, and how follow-up X-ray reviews and frame removal are handled. Ask for that list in writing. A figure worth comparing comes after a surgeon has read your scans, and that review is free.
Complex trauma reconstruction FAQ
Can a fracture that has not healed for a year still heal?
Yes. Published union rates for tibial nonunions treated with a new nail or a circular frame run from 88 to 97 percent in a systematic review of 26 studies.
How long will I wear an external frame?
For bone transport in the tibia, a mean of 11 months in a review of 3,543 adults. Shorter corrections need less time.
Do I have to stay in Turkey for the whole treatment?
No. After the first two to three weeks, X-rays taken near home go to the surgeon by WhatsApp, and you return for frame removal or a planned second stage.
Can a family member stay with me in the hospital?
Yes. The patient room has a companion bed for the whole admission, and that family member is taught the pin care and frame adjustments before discharge.
What should I send for a free review?
X-rays of the whole bone from the front and the side, older X-rays from each stage of treatment, any CT or MRI, the operation notes, photographs of the wound or scar, any culture results, recent C-reactive protein, and a list of medications and illnesses such as diabetes. An orthopedic trauma surgeon replies with the problem as it appears, the likely method, the number of stages and the expected stay, at no charge and with no obligation to travel.
References
Fortuin F, Burger M, Ferreira N. Contemporary management of aseptic diaphyseal tibia non-unions. A systematic review. Orthop Traumatol Surg Res. 2022;108(5):102990.
Bezstarosti H, Metsemakers WJ, van Lieshout EMM, et al. Management of critical-sized bone defects in the treatment of fracture-related infection: a systematic review and pooled analysis. Arch Orthop Trauma Surg. 2021;141(7):1215-1230.
Lima JPC, Chagas KA, Oliveira LBP, et al. Oral versus intravenous antibiotics for bone and joint infections: systematic review and meta-analysis of randomized controlled trials. Bone. 2025;196:117494.
Wakefield SM, Papakostidis C, Giannoudis VP, et al. Distraction osteogenesis versus induced membrane technique for infected tibial non-unions with segmental bone loss: a systematic review of the literature and meta-analysis of available studies. Eur J Trauma Emerg Surg. 2024;50(3):705-721.
Giuli C, Di Pietro G, Farine F, et al. Tibial bone transport using external fixation in adults: a systematic review. Arch Orthop Trauma Surg. 2026;146(1). doi:10.1007/s00402-026-06438-6
Salimi J, Soltani Asl Heris S, Shokri A, et al. Limb salvage versus primary amputation in severe lower extremity trauma: a systematic review and meta-analysis. Trauma Surg Acute Care Open. 2026;11(3):e002211.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Assistant Professor Şafak SAYAR, Orthopedics and Traumatology.