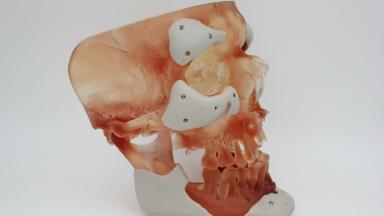
Infection now causes more failed knee replacements than any other single reason, 21.6 percent across registries in seven countries, and it can turn a revision into two operations with weeks of antibiotics between them. This page explains how the cause is found before surgery, when cones or a hinge are needed, and how a two-stage revision fits around travel.
About This Department
Orthopedics
A second knee operation starts with one question, why the first knee failed. The answer decides everything after it.
Complex knee revision surgery replaces a failed knee replacement when bone has worn away, the ligaments no longer hold the joint, or an infection has to be cleared before anything new goes in. The porous metal cones now used to rebuild lost bone grew into the patient's own bone in 96 percent of cases across 4,433 patients in a 2026 meta-analysis. This page covers how the cause is found, what one-stage and two-stage revision involve, how long the trip to Istanbul runs, and which records to send for a free review.
21.6%
Knee revisions done for infection, registries in seven countries
96%
Porous cones grown into bone, 4,433 patients
91.6%
Hinged revision knees still in place at five years
A knee revision takes out part or all of a knee replacement and puts in a new one.
Surgeons call it complex when the second operation has to solve a problem the first one never faced, and those problems come in a handful of familiar forms, starting with bone that has worn away around a loose implant and left cavities that standard components cannot sit on. Ligaments stretched over years stop holding the joint steady. The new knee then has to supply that stability itself. Infection changes the whole plan. Bacteria live in a film on the metal surface and the old implant has to come out before the knee can be rebuilt. Earlier revisions, a stiff knee that bends less than ninety degrees, a fracture around the implant and a damaged kneecap tendon all add to the list, and many patients arrive with two or three of these at once. Across national joint registries in seven countries, deep infection accounted for 21.6 percent of knee revisions, loosening without infection for 18.3 percent, instability for 14.1 percent and unexplained pain for 10.9 percent.
Pain alone, with a well-fixed implant and no infection, makes the weakest case for revision.
Finding out why the first knee failed
Every revision plan starts from a diagnosis, and the tests come long before an operating date, with infection ruled out first in every case, even when the knee looks clean and the wound healed well years ago.
Blood tests. C-reactive protein and the erythrocyte sedimentation rate rise with inflammation, and two normal results make infection less likely without excluding it.
Fluid from the joint. A needle draws fluid from the knee for a white cell count and a culture, ideally after two weeks off antibiotics so that any bacteria can still grow.
Imaging. Standing X-rays of the whole leg show alignment and loosening, and a CT scan measures bone loss and the rotation of the old components.
Caution here comes from the numbers. A 2023 systematic review of 5,821 revisions planned as infection-free found unexpected positive cultures in 14 percent of them, two thirds of those from a single sample of a low-grade organism, and after a knee revision a single result of that kind behaved like contamination in most of the studies.
Two positives change the plan.
When the cause is infection
Across 83,353 patients in a 2026 meta-analysis, 13.3 percent of those with an infected knee replacement had died at a mean follow-up of 4.4 years, a higher figure than five-year mortality from breast or prostate cancer, and so infected revision gets treated as a medical illness as well as an operation, with the surgeon and an infectious diseases physician writing the antibiotic plan together.
Two-stage revision
The first operation removes every component and all the old cement, cuts away infected tissue, and fills the space with a spacer of bone cement loaded with antibiotics. Six weeks of antibiotics follow, through a vein at first and as tablets later in many protocols, and once blood tests and sometimes a second joint sample confirm the infection has settled, the new implant goes in at a second operation, commonly two to three months after the first.
One-stage revision
Removal, cleaning and the new implant all happen under one anesthetic. It suits a selected group. That means an organism identified before surgery that standard antibiotics kill, healthy skin and muscle around the knee, and a patient fit enough for a long operation. In the same 2026 meta-analysis, mortality after one-stage exchange was 0.47 percent against 11.5 percent after two-stage, a gap that reflects in large part the fitter patients chosen for a single stage.
The culture result decides which route applies.
Rebuilding lost bone
Bone loss looks small on an X-ray and large in the operating room.
Once the old implant and its cement come out, the surgeon measures what is left at the end of the thigh bone and the top of the shin bone and fills each defect with something strong enough to carry body weight for decades. Small holes take cement, sometimes reinforced with screws. Shallow loss under one side of a component takes a metal block or wedge bolted to the implant. Deep cavities in the wide end of the bone, the part surgeons call the metaphysis, take a porous metal cone or a sleeve, and both work by giving bone a rough metal surface it can grow into. Long stems pushed into the shaft of the bone spread the load further away from the damaged area, and in the worst cases, with whole segments missing after several failed operations, donor bone or a custom implant replaces what has gone.
This table scrolls sideways on a narrow screen. Swipe or drag to see every column.
Ways to fill a bone defect in a knee revision
Option
Used for
Published results
Cement and screws
Small contained holes
A long-standing technique for minor defects
Metal blocks and wedges
Shallow loss under one side of a component
Part of every modern revision system, used with stems
Porous metal cones
Deep cavities in the wide end of the bone
96% grown into bone and 0.7% removed for loosening, 63 studies, 4,433 patients
Metaphyseal sleeves
Deep cavities, press-fitted onto the implant stem
0.4% loosening without infection in studies following knees for five years or more
The 2026 cone meta-analysis covered 63 studies and found re-revision for any reason in 13.5 percent at a mean follow-up of 49.7 months, most of it for infection, while loosening of the cone itself was rare. A meta-analysis of 3,008 revisions put periprosthetic infection at 11.7 percent with cones and 4.9 percent with sleeves at long-term follow-up, and the authors noted that cones had been used more often with hinged implants, which means in the more damaged knees.
How much stability the new knee supplies
A first knee replacement relies on the patient's own ligaments to keep the joint from wobbling, while in a revision those ligaments may be stretched, scarred or gone and the implant has to make up the difference. A constrained condylar knee uses a tall post on the plastic insert that sits in a deep box on the thigh component and blocks side-to-side movement, and a rotating hinge joins the thigh and shin components with an axle, so the knee stays stable even with no working side ligaments at all. Surgeons choose the least constraint that keeps the knee steady, because every step up in constraint passes more of the twisting force from each stride into the fixation of the implant in bone, and so hinged and highly constrained knees almost always come with long stems and often with cones or sleeves as well. The choice gets made in two stages, first on the CT scan and then again in the operating room, where the surgeon tests how the knee behaves once the old implant is out and the trial components are in.
In a 2023 meta-analysis of 4,555 revision knees, five-year survival reached 91.6 percent with rotating hinges and 89.8 percent with constrained condylar designs, a difference that was not significant.
Both groups ended with an average bend of 105 degrees. Stiffness is where the hinge pulls ahead. Across seven studies of revision for a stiff, scarred knee, a 2026 meta-analysis found that rotating hinge implants improved the range of motion by 42.2 degrees on average and by 17.5 degrees more than non-hinged revision designs, with no rise in complications.
Who should wait before traveling
Travel suits a patient whose cause of failure has been found, or can be found from the records, and whose general health is stable. Some situations call for treatment at home first.
A hot, swollen knee with fever, or pus draining from the wound, which needs surgery within days, close to home
A blood clot in the leg or lung within the past three months
Diabetes with blood sugar out of control, since high sugar raises the risk of a new infection
Heart or lung disease that has not yet been assessed for a three to four hour anesthetic
Smoking within the past four weeks, which slows wound healing
Anyone who recognizes themselves in that list can still send the file, and the reply says what needs settling first at home and when the trip would make sense.
The operation and the hospital stay
Surgery day
Admission comes the day before surgery. Blood tests, a review by the anesthetist and a chest X-ray fill that afternoon. The operation takes three to four hours for a single-stage revision and runs longer when cones, a hinge or a muscle flap to cover the wound are needed. Samples of tissue from around the old implant go to the laboratory during the operation, five or more of them by standard practice, because those results confirm or exclude infection one final time. Physiotherapy starts the next day. Standing comes first, then a few steps on a walker. Blood-thinning injections begin the same evening. Packages published by Istanbul hospitals plan four to five nights on the ward for a single-stage revision and up to ten nights for an infected two-stage case, with the antibiotics given through a vein while you are in hospital. The patient room has a companion bed, so one family member stays overnight for the whole admission.
Recovery, week by week
Recovery from complex knee revision surgery runs slower than recovery from a first knee replacement, because more tissue has been disturbed and the bone needs time to grow into the new metal.
This table scrolls sideways on a narrow screen. Swipe or drag to see every column.
A single-stage revision timeline
When
What happens
What you can do
Weeks 1 and 2
Daily physiotherapy, wound checks, stitches or clips out at around 14 days
Walk with a frame or two crutches, bend the knee to 90 degrees
Weeks 3 to 6
Exercises continue with a physiotherapist at home, blood thinners finish
Stairs one at a time, short walks outdoors
Weeks 6 to 12
X-ray at six weeks, strength work for the thigh muscles
One stick or none, desk work, driving once the surgeon agrees
Months 3 to 12
Swelling fades, bone grows into cones or sleeves
Longer walks, swimming, cycling
The first year
Warmth and swelling around a revised knee last up to a full year.
Two weeks in Istanbul, then the flight
Medical travel listings for knee revision in Istanbul plan 14 days in the country, and the flight home follows the wound check and removal of stitches at around two weeks. Blood-thinning injections continue on the day you fly. An aisle seat, compression stockings and a walk along the aisle every hour lower the risk of a clot. After the four to five nights on the ward, the remaining nights are spent in a hotel near the hospital, arranged by the international patients office along with airport transfers and transport to each physiotherapy session.
Physiotherapy carries on every day at the hospital during the hotel nights. Before you leave, the same physiotherapist writes the home program, with the exercises, the target bend for each week, and the point at which the walker gives way to crutches and the crutches to a single stick.
Two stages, two trips.
The spacer stays in for six weeks or more while the antibiotics run, and many patients go back home in between with the antibiotic plan and the blood test schedule written out for their own doctor, then return for the second operation and a further two weeks. A coordinator assigned from the first message stays in touch through both stages, on WhatsApp and in English, Arabic, French, Russian, Serbian, Romanian or Spanish, and interpreting in other languages is arranged on request so that the consent conversation about infection and re-revision happens in your own language. A request for a female surgeon goes to the department and is met wherever the rota allows. Halal, vegetarian and diabetic meals come from the hospital kitchen, a prayer room is on site, and the invitation letter naming the hospital and the surgeon goes out ten days before travel for the visa application.
What changes the quote
One stage or two sets most of the cost.
A two-stage revision means two operations, a spacer, weeks of antibiotics and a longer stay. After that come the parts the new knee needs. Cones or sleeves, metal blocks, long stems and a rotating hinge each add to the implant bill, and the surgeon settles the final mix only once the old implant is out. Intensive care nights, blood transfusion, a muscle flap to close the wound and the number of physiotherapy sessions all move the total. Your own health matters as well. Diabetes, a high body weight, heart or kidney disease and blood thinners taken for another condition can lengthen the stay.
Packages for knee revision in this market include the surgeon and anesthesia fees, the implant, the nights on the ward, intravenous antibiotics, physiotherapy, an interpreter and airport transfers, and some list a set number of physiotherapy sessions, while flights, travel insurance, extra hospital nights, the treatment of a complication and in many cases the hotel stay outside them. Before comparing two offers, find out whether the figure assumes one stage or two, whether cones, sleeves or a hinge are inside it, which implant brand it names, whether the tissue cultures are covered, and what happens financially if the culture result turns a one-stage plan into a two-stage one. A figure worth comparing comes only after a surgeon has read your X-rays, scans and test results, and that review is free.
Once you are home
X-rays at six weeks, one year and then every year or two show whether the implant is fixed and whether bone has grown into the cones or sleeves. Local clinics take them. They go by WhatsApp to the same coordinator, and the surgeon who operated compares them with the images taken before you left. A physiotherapist near home carries on the program from the discharge letter, and dentists and other surgeons should hear about the revised knee before any procedure.
Get in touch the same day if any of these appear.
Fever, or fluid leaking from the wound after the first week
A knee that becomes hotter, redder or more painful after it had been settling
A swollen, tender calf, chest pain or sudden breathlessness
The knee giving way, or a new clunk when walking
A local emergency department does the first assessment. The surgeon speaks to that doctor directly with the operation note to hand.
Complex knee revision surgery FAQ
How long does a revision knee replacement last?
In a 2023 meta-analysis of 4,555 revision knees, 91.6 percent of rotating hinges and 89.8 percent of constrained condylar knees were still in place at five years. Infection causes most later failures.
How long do I need to stay in Turkey?
Two weeks for a single-stage revision, with four to five nights in hospital and the rest in a hotel. The flight home follows the wound check at around 14 days.
How long is the gap between the two stages for an infected knee?
The antibiotic spacer stays in for six weeks or more, and the second operation goes ahead two to three months after the first once blood tests show the infection has settled. Many patients spend the interval at home.
Can a family member stay in the hospital with me?
Yes. The patient room has a companion bed for the whole admission.
What should I send for a free review?
Standing X-rays of the knee from the front and the side, any CT scan, the operation notes from earlier knee surgery including the implant labels if you have them, recent C-reactive protein and sedimentation rate results, any joint fluid culture, and a list of current medications. An orthopedic surgeon reads the file and replies with the likely cause of failure, whether one stage or two would be planned, how long the stay would be and which further tests are needed, at no charge and with no obligation to travel.
References
Hauer G, Rasic L, Klim S, et al. Septic complications are on the rise and aseptic loosening has decreased in total joint arthroplasty: an updated complication based analysis using worldwide arthroplasty registers. Arch Orthop Trauma Surg. 2024;144(12):5199-5204.
Schwarze J, Moellenbeck B, Gosheger G, et al. The role of single positive cultures in presumed aseptic total hip and knee revision surgery: a systematic review of the literature. Diagnostics (Basel). 2023;13(9):1655.
Ramos MS, Benyamini B, Kompala V, et al. Mortality after an infected total knee arthroplasty: a meta-analysis. Bone Joint J. 2026;108-B(2):177-184.
Goh GS, Lee S, Singh K, et al. Contemporary outcomes of highly porous metaphyseal cones in revision total knee arthroplasty: a systematic review and meta-analysis. J Arthroplasty. 2026;41(10):3210-3230.e16.
Fischer LT, Heinecke M, Rohner E, et al. Cones and sleeves present good survival and clinical outcome in revision total knee arthroplasty: a meta-analysis. Knee Surg Sports Traumatol Arthrosc. 2022;30(8):2824-2837.
Stroobant L, de Taeye T, Byttebier P, et al. Condylar constrained and rotating hinged implants in revision knee arthroplasty show similar survivorship and clinical outcome: a systematic review and meta-analysis. Knee Surg Sports Traumatol Arthrosc. 2023;31(12):5365-5380.
Ruelos VCB, Jayarajan NA, Shi JL, et al. Rotating-hinge revision total knee arthroplasty for arthrofibrosis improves motion without increasing complications: a systematic review and meta-analysis. J Arthroplasty. 2026. doi:10.1016/j.arth.2026.06.041
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Assoc. Prof. Dr. Necdet DEMİR, Orthopedics and Traumatology.