Arthroscopic Surgery - Minimally Invasive Joint Surgery
Two or three cuts of about a centimeter, a camera inside the joint and fine instruments let surgeons repair torn ligaments, cartilage and unstable shoulders with less pain than open surgery. This guide covers the knee, shoulder, hip, ankle, wrist and elbow, where the randomized trials show arthroscopy helps and where they show it does not, how the operation is done, the risks, the recovery and how long to stay in Istanbul.
About This Department
Orthopedics
Small cuts, a camera, a repaired joint. Best for injuries, less so for wear.
In a trial of 348 patients with hip impingement, arthroscopy improved hip-related quality of life more than a physiotherapy program, by a margin patients notice.
1 cm
Typical length of each arthroscopy cut
6.8 points
Hip quality of life gain over physiotherapy in UK FASHIoN
1 day
Hospital stay in a published Istanbul knee arthroscopy package
Free
Review of your MRI before you book
Free consultation
The review costs nothing and carries no obligation. Send your MRI, X-rays and a short description of the injury and your symptoms, and our orthopedic team will tell you whether arthroscopy fits the problem, what repair to expect, and how long to plan for. A coordinator replies in your own language.
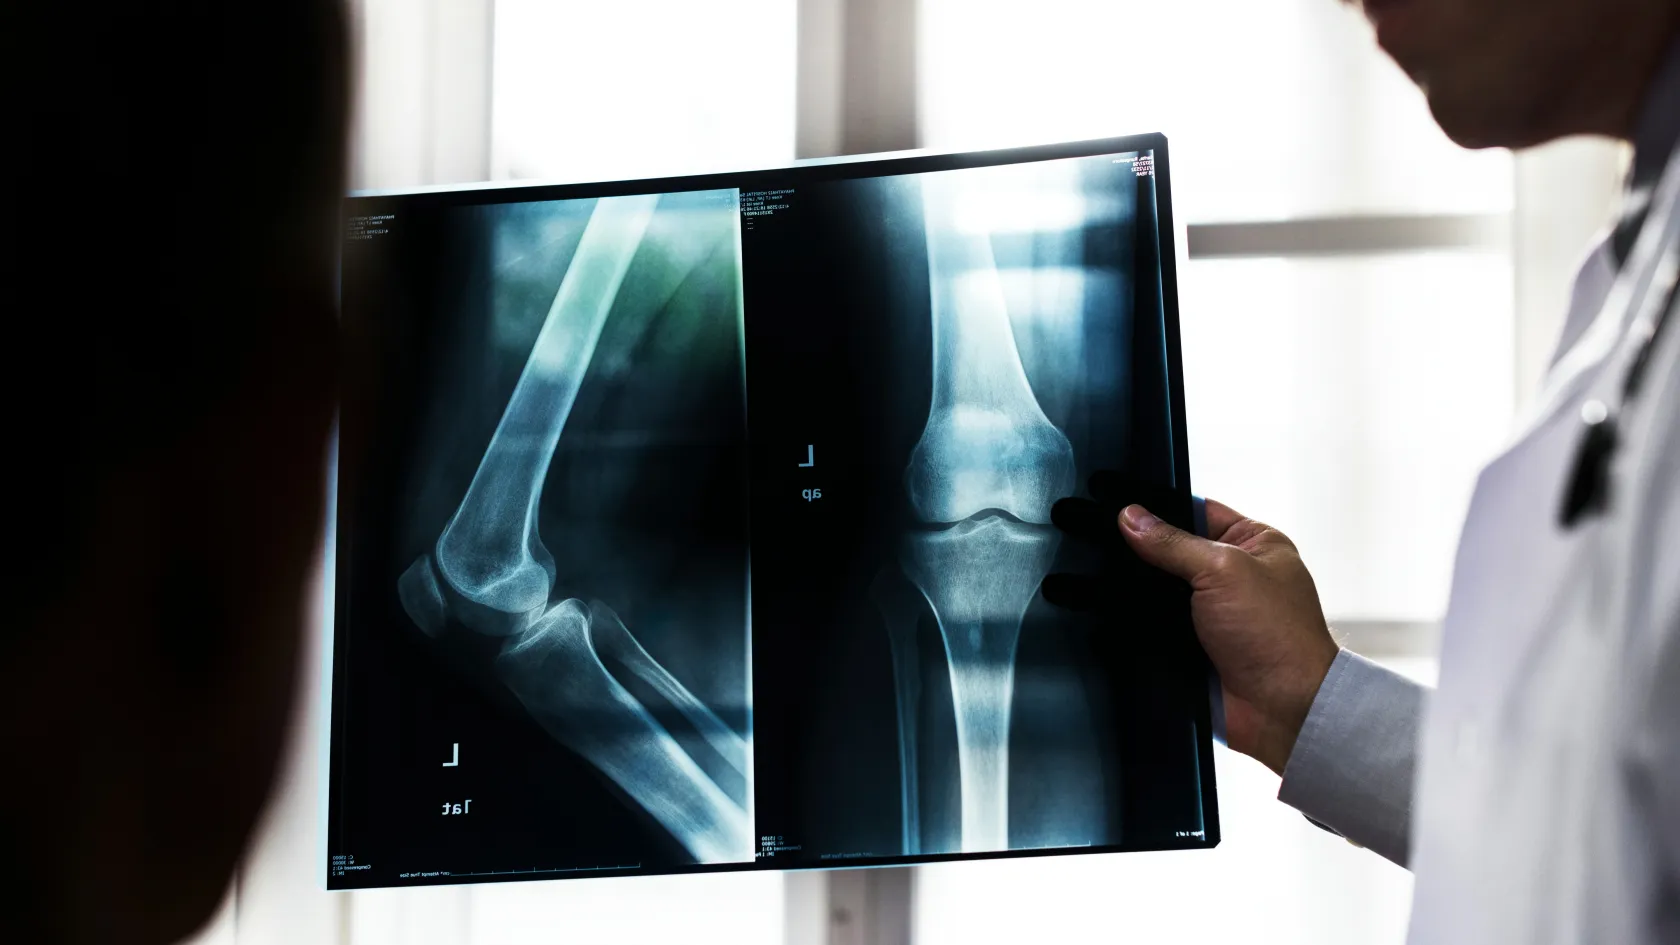
A knee that locks or gives way after a twist, a shoulder that slips out of its socket, a hip that pinches when you sit. Rest and physiotherapy have not settled it. Arthroscopic surgery looks inside the joint through a camera the width of a pencil and repairs it through two or three cuts of about a centimeter each, with less pain and a faster return to daily life than open surgery. Below you will find which joints and problems it treats, where the randomized trials show it helps and where they show it does not, how it is done, the risks, the recovery, how long to stay in Istanbul, and the follow-up at home.
What arthroscopy is
Small cuts, a camera and a screen.
The joint is repaired from inside, with the muscles around it left in place.
The surgeon fills the joint with sterile saline so it expands, passes a small camera called an arthroscope through one tiny cut, and watches a magnified picture of the cartilage, ligaments and lining on a screen. Fine instruments enter through one or two other cuts to trim, stitch, anchor or rebuild what is damaged. The knee and shoulder are the most common joints treated this way, followed by the hip, ankle, wrist and elbow. Most operations take thirty minutes to two hours under general or spinal anesthesia, and many patients go home the same day or the next morning with small dressings and stitches or strips over the cuts. Compared with opening the joint, the muscles and tendons around it stay largely untouched, which is why pain is lower and movement returns sooner. The images from inside are saved and shared with you afterward, so you can see the torn ligament, the cartilage flap or the loose fragment and what was done about it.
This table scrolls sideways on a narrow screen. Swipe or drag to see every column.
Common arthroscopic operations by joint
Joint
Common operations
Typical problems
Knee
ACL reconstruction, meniscus repair, cartilage repair, removal of loose bodies
Sports injuries, locking, giving way
Shoulder
Stabilization, rotator cuff repair, release of a frozen shoulder
Dislocations, cuff tears, stiffness
Hip
Reshaping the bone, labral repair
Femoroacetabular impingement in younger adults
Ankle
Removal of bone spurs, cartilage repair, ligament stabilization
Impingement, cartilage lesions, instability
Wrist and elbow
Cartilage and ligament repair, loose body removal
Injuries, locking, stiffness
Signs of a mechanical problem inside a joint include
locking or catching,
giving way on turning,
a shoulder that slips out,
and swelling that returns after activity.
Is arthroscopy the same as keyhole or minimally invasive joint surgery?
Yes. Arthroscopy is the medical name for keyhole joint surgery, and minimally invasive joint surgery covers it along with small-incision open techniques.
Where it helps
Ligament and cartilage injuries
Arthroscopy works best for a mechanical problem with a clear structural cause, such as
a torn anterior cruciate ligament in someone who wants to return to pivoting sports,
a meniscus tear from an injury in a younger knee, which can often be stitched,
a shoulder that dislocates again and again,
a large rotator cuff tear with weakness,
a loose fragment that locks the joint,
and a hip with impingement from an abnormally shaped bone.
ACL tears and timing
In a Swedish trial of 121 young, active adults with a torn ACL, early reconstruction plus rehabilitation gave the same knee scores at two years as rehabilitation with the option of later surgery, and in that second group only 23 of 59 eventually chose reconstruction. Rehabilitation comes first, and reconstruction follows for knees that keep giving way or for athletes returning to pivoting sports.
Rehabilitation first, reconstruction for knees that keep giving way.
Hip impingement
In the UK FASHIoN trial of 348 patients with hip impingement, hip-related quality of life scores rose from 39.2 to 58.8 at one year after arthroscopy and from 35.6 to 49.7 after a physiotherapist-led program, a difference of 6.8 points in favor of surgery that passed the threshold patients notice.
The best results come from fixing a clear mechanical fault.
Where it does not help
Worn joints are different. For a knee with osteoarthritis, or a meniscus that has frayed with age rather than torn in an injury, washing out and trimming the joint gives no lasting benefit, and an international guideline published in the BMJ in 2017 recommends against arthroscopy for nearly all patients with degenerative knee disease. The key trial was blind. In a Finnish study of 146 people aged 35 to 65 with a degenerative meniscus tear and no arthritis, trimming the meniscus improved knee scores by 21.7 points at one year, while a sham operation in which nothing was trimmed improved them by 23.3 points, so the real operation added nothing.
Scroll sideways on small screens to see every column.
Randomized trials that shaped arthroscopic practice
Trial
Patients
Finding
Degenerative meniscus, 2013
146
Partial meniscectomy no better than sham surgery at one year
Shoulder decompression, CSAW, 2018
313
Removing bone spurs added nothing over a diagnostic arthroscopy
Acute ACL tear, 2010
121
Early reconstruction no better than rehabilitation with optional later surgery
Hip impingement, UK FASHIoN, 2018
348
Arthroscopy better than physiotherapy by a clinically meaningful margin
For worn knees, the guideline favors
exercise therapy and physiotherapy,
weight loss where needed,
pain relief and, for some, injections,
and joint replacement when these no longer help.
Shoulder pain without a tear
In CSAW, 313 people with shoulder pain and an intact rotator cuff were randomized to subacromial decompression, an arthroscopy in which nothing was removed, or no treatment. Shoulder scores at six months were similar after both operations, and their small advantage over no treatment was too small to matter to patients.
How the operation is done
1
Anesthesia
General or spinal anesthesia, often with a nerve block that keeps the joint comfortable for the first hours.
2
Small cuts
Two to four cuts of about a centimeter around the joint.
3
Inspection
The whole joint is examined on screen, cartilage, ligaments and lining in turn, and the findings are saved as pictures you can keep.
4
Repair
Stitches, anchors, grafts or trimming, depending on what the camera shows.
5
Closing
Each cut is closed with a stitch or strip, and a brace or sling is fitted where needed.
Day surgery or one night
Most arthroscopies are day cases. ACL reconstruction, shoulder stabilization and hip arthroscopy often keep you one night for pain control and the first physiotherapy session.
Signs it may be time
A clear injury on examination and MRI, symptoms such as locking, giving way or repeated dislocation, failure of a proper course of physiotherapy, and goals that depend on a stable joint.
Talk to us first
Knee osteoarthritis or a meniscus worn with age, shoulder pain without a tear that has not had a full rehabilitation program, or expectations that the operation will reverse joint wear.
Risks and how they are managed
1
Before surgery
Skin, blood tests and clot risk are checked, and blood thinners are planned.
2
In the operating room
Antibiotics before the first cut, and a sterile field throughout.
3
Afterward
Walking the same day, exercises from the first day, and a wound check before you fly.
Swelling and stiffness
The most common problems, eased with ice, elevation and early exercises.
Infection
Rare after arthroscopy. Antibiotics at the start of surgery and sterile technique keep it low.
Blood clots
Uncommon. Early walking and, after knee and hip surgery in patients at higher risk, clot prevention medicine.
Graft or repair failure
A reconstructed ligament or stitched meniscus can tear again, more often with an early return to sport, which is why rehabilitation milestones matter.
The recovery
The repair sets the pace, more than the size of the cuts. After removal of a loose fragment, walking returns within days and work within a week or two. A stitched meniscus is different, needing crutches and a hinged brace for four to six weeks because the stitches must hold while the tissue knits, and an ACL reconstruction takes six to nine months before pivoting sports, with the decision to return guided by strength, balance and hop tests that compare the operated leg with the other one. After shoulder stabilization or cuff repair, the arm rests in a sling for four to six weeks. Full strength takes four to six months. Hip arthroscopy patients use crutches for two to four weeks and avoid deep sitting at first. Swelling settles over a few weeks, ice and elevation help, and the small scars fade over months. Physiotherapy starts within days and decides most of the result.
How long to stay in Istanbul
Plan on five to seven days.
Published Istanbul knee arthroscopy packages list one day in hospital and include consultations, preoperative and blood tests, an orthopedic surgeon's review, language assistance and airport transfers. Then come a wound check and the first physiotherapy sessions. ACL and shoulder repairs benefit from a full week, so that the home exercise plan is learned well before the flight. Fitness to fly is confirmed at the final visit, and long flights after knee or hip surgery call for an aisle seat, ankle exercises and regular walks.
What decides the cost
The joint, the repair, any graft or anchors, the type of anesthesia, nights in hospital and physiotherapy sessions set most of the figure.
A quote you can compare names the joint, the planned repair and the stay. That figure comes only after an orthopedic surgeon reviews your MRI and examination findings, and the review costs nothing.
Arranging the trip
An MRI and a short note on how the injury happened, sent on WhatsApp, start the review, and the coordinator who answers stays with you through surgery and the first weeks of physiotherapy at home. You can speak English, Arabic, French, Russian, Serbian, Romanian or Spanish with the team, and interpreters cover other languages. Someone close to you can sleep on the companion bed in your room. Hotel nights, the visa invitation letter sent ten days before travel and the transfers are handled by the international office, and the hospital serves halal, vegetarian and diabetic meals, with a prayer room and a female physician on request.
Once you are back home
Your physiotherapist near home continues the program, with videos of your progress sent to the Istanbul team through the coordinator at two, six and twelve weeks.
Fever, a red, hot or leaking wound, a swollen and painful calf, sudden breathlessness, or a joint that suddenly swells and locks. Each needs a doctor the same day.
Arthroscopic surgery FAQ
How long does arthroscopic surgery take?
Thirty minutes to two hours, depending on the joint and the repair.
Is arthroscopy useful for knee arthritis?
No. Trials and an international guideline found no lasting benefit for worn knees.
When can I walk after knee arthroscopy?
The same day after simple procedures, and with crutches for some weeks after a meniscus repair or ligament reconstruction.
Will I have scars?
Two to four small scars of about a centimeter each, which fade over months.
Does an ACL tear always need surgery?
No. In one trial, fewer than half of those offered rehabilitation first went on to need reconstruction.
Can a family member stay with me?
Yes. One person can stay overnight in your room on the companion bed, and the international office finds a hotel nearby for anyone else.
References
Sihvonen R, Paavola M, Malmivaara A, et al. Arthroscopic partial meniscectomy versus sham surgery for a degenerative meniscal tear. N Engl J Med. 2013;369(26):2515-2524.
Siemieniuk RAC, Harris IA, Agoritsas T, et al. Arthroscopic surgery for degenerative knee arthritis and meniscal tears. A clinical practice guideline. BMJ. 2017;357:j1982.
Frobell RB, Roos EM, Roos HP, Ranstam J, Lohmander LS. A randomized trial of treatment for acute anterior cruciate ligament tears. N Engl J Med. 2010;363(4):331-342.
Beard DJ, Rees JL, Cook JA, et al. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW), a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet. 2018;391(10118):329-338.
Griffin DR, Dickenson EJ, Wall PDH, et al. Hip arthroscopy versus best conservative care for the treatment of femoroacetabular impingement syndrome (UK FASHIoN). A multicentre randomised controlled trial. Lancet. 2018;391(10136):2225-2235.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Assistant Professor Şafak SAYAR, Orthopedics and Traumatology.