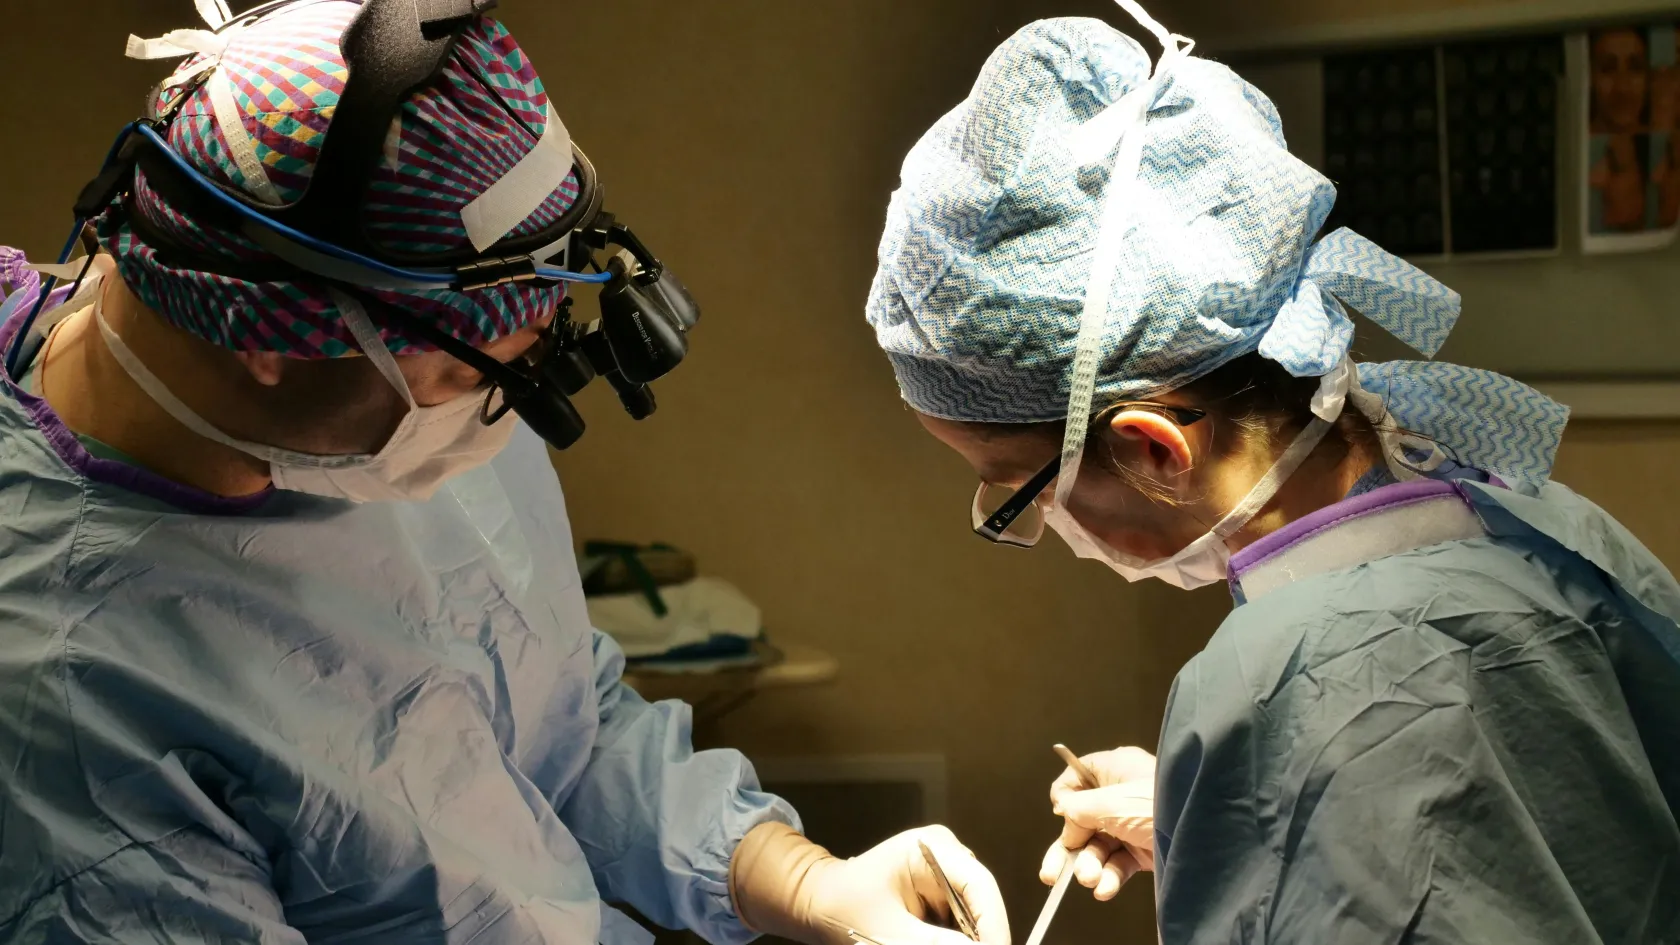
Nephrectomy in a child removes all or part of a kidney that no longer works and causes infections, pain or high blood pressure, or a kidney with a Wilms tumor. Most benign operations are done by keyhole surgery with one to two days in hospital, and partial nephrectomy keeps healthy kidney tissue whenever possible. At Biruni Hospital in Istanbul, our pediatric urology team plans each operation, and our nephrologists follow children with one kidney for life.
About This Department
Pediatric Urology
Children live well with one healthy kidney. Nephrectomy removes a kidney that harms more than it helps, or one that holds a tumor.
Nephrectomy in a child removes all or part of a kidney. For benign conditions the kidney has stopped working and causes infections, pain or high blood pressure, from blockage, severe reflux or a malformation present from birth, and for cancer the operation removes a Wilms tumor, the most common kidney cancer of childhood. Keyhole surgery has become the standard for benign kidneys. In a London series of 213 children, complications during surgery were more frequent with open operations, and no retroperitoneoscopic operation needed conversion to open surgery (Mosa and colleagues, Journal of Laparoendoscopic and Advanced Surgical Techniques, 2021). For Wilms tumor, a 2025 meta-analysis found similar tumor spill, recurrence and survival after keyhole and open nephrectomy in selected children. Keyhole surgery sampled fewer lymph nodes (Pio and colleagues, Pediatric Surgery International, 2025). This page explains reasons for nephrectomy, tests, partial nephrectomy, keyhole and open techniques, Wilms tumor surgery, recovery, life with one kidney, and how families from abroad arrange kidney removal surgery for a child at Biruni Hospital in Istanbul.
213
Children in a series comparing keyhole and open nephrectomy, with fewer complications by keyhole
90
Percent or more of children cured of Wilms tumor with surgery and chemotherapy
657
Children with Wilms tumor treated by partial nephrectomy in a 26-study review
Free
Review of your child's scans and kidney function tests by our pediatric urology team
A single healthy kidney grows larger and takes over the work of both. Children with one kidney grow, play and live a full life.
Pediatric urologists and pediatric surgeons perform these operations, with pediatric nephrologists and, for tumors, pediatric oncologists in the same team.
Removal is the last step. Before any decision we measure how much the kidney still contributes and whether surgery to repair it would help more.
Who is involved
Specialist
Role
When
Pediatric urologist or surgeon
Plans and performs the operation
Throughout
Pediatric nephrologist
Kidney function and blood pressure
Before and for years after
Pediatric radiologist
Ultrasound, MRI, nuclear scans
Before surgery
Reasons to remove a kidney
Benign conditions that lead to nephrectomy
Condition
What happens
When surgery helps
Long-standing blockage
Kidney damaged by obstruction at the pelvis or ureter
Under 10 percent function, infections or pain
Severe reflux
Scarred kidney, repeated fever infections
Non-working kidney with infections
Multicystic dysplastic kidney
Kidney of cysts with no function
Growth, high blood pressure, rarely
Renovascular hypertension
Small kidney driving blood pressure up
Medicines fail
Before kidney transplant
Some children need one or both native kidneys removed before a transplant, for example very large polycystic kidneys, congenital nephrotic syndrome with heavy protein loss, or kidneys with repeated infections. Our pediatric kidney transplant page explains the full transplant pathway.
Other reasons
Reason
Example
Approach
Stones
Kidney destroyed by stones and infection
Keyhole nephrectomy
Injury
Severe trauma with bleeding
Repair first, removal if needed
Tumor
Wilms and other kidney tumors
Radical or partial nephrectomy
Does a multicystic dysplastic kidney always need removal?
No. Most shrink by themselves over the first years of life and are followed by ultrasound. We remove them when they keep growing, cause high blood pressure or press on nearby organs, and the operation is a small keyhole procedure.
Watching first
Many non-working kidneys cause no symptoms, and we follow them with ultrasound and blood pressure checks instead of removing them.
Tests before the decision
Measuring function
The DMSA scan shows how much each kidney contributes. A kidney giving under ten percent of total function rarely recovers.
Tests before nephrectomy
Test
What it shows
Note
Ultrasound
Size, cysts, swelling, the other kidney
First test
DMSA or MAG3 scan
Split function, drainage
Nuclear medicine
Voiding cystourethrogram
Reflux into the ureters
When reflux suspected
MRI or CT
Tumors, anatomy, vessels
For tumors and complex cases
The other kidney gets the same careful look. Removal is planned only when it is healthy.
Blood tests check kidney function, blood count and clotting, and urine tests look for infection and protein. Blood pressure is measured on several days.
Family discussion
1
The plan in writing
We explain the findings, the options including watching or repair, and the reasons for removal, and give the family a written summary.
Partial nephrectomy
1
Duplex kidneys
Some children have a kidney with two drainage systems. One part, often the upper one, may not work and drains through an ectopic ureter or a ureterocele, causing infections or constant dribbling in girls.
Heminephrectomy removes only the non-working part and its ureter by keyhole surgery, keeping the healthy part of the kidney. Care at the cut surface protects the blood supply of the part that stays.
2
Other options
A small endoscopic puncture of a ureterocele, or joining the two ureters, can be enough for some children, and we compare these with partial removal.
Can the remaining part of the kidney be harmed?
A small loss of function in the remaining part occurs in a minority of children, mostly in infants. Careful handling of the shared vessels, magnification and experience keep the risk low, and a DMSA scan after six months checks the result.
Kidneys we try to keep
Removal cannot be reversed.
Before recommending nephrectomy we look for every way to save kidney tissue, by repairing a blockage with pyeloplasty, treating reflux with an endoscopic injection or reimplantation, removing only the non-working part of a duplex kidney, or, in Wilms tumor that affects both kidneys or a single kidney, removing the tumor and leaving the rest, because every nephron matters across a lifetime and a child with two working kidneys has a larger reserve for illness, injury or pregnancy later in life. When function has gone and the kidney causes harm, we recommend removal.
We explain both paths and give the family time.
Keyhole or open surgery
Nephrectomy approaches in 213 children
Approach
Conversion to open
Complications
Retroperitoneoscopic, from the back
None
Rare
Transperitoneal laparoscopic
5.4 percent
Rare
Open
Not applicable
More frequent during surgery
Keyhole nephrectomy uses three small cuts and a camera. The retroperitoneal route reaches the kidney from the back without entering the abdominal cavity, while the transperitoneal route goes through the abdomen and allows removal of the whole ureter down to the bladder (Mosa and colleagues, 2021).
Choosing the route
Situation
Preferred route
Reason
Non-working kidney, no reflux
Retroperitoneoscopic
Quick recovery
Reflux into the ureter
Transperitoneal laparoscopic
Removes the full ureter
Large tumor, earlier surgery
Open
Safety and complete removal
Children go home one to two days after keyhole nephrectomy for benign disease.
Wilms tumor
Wilms tumor, also called nephroblastoma, is cured in more than nine of ten children with surgery and chemotherapy, and in some with radiotherapy.
Two international approaches to Wilms tumor
Approach
First step
Used in
SIOP
Four weeks of chemotherapy before surgery
Europe and most of the world
COG
Surgery first in most children
North America
Both
Chemotherapy after surgery by stage and histology
Worldwide
Wilms tumor affects one in 10,000 children, peaks between ages two and five and presents as a swollen belly or a lump found while bathing the child. Blood in the urine and high blood pressure occur in some. Imaging of the abdomen and chest stages the disease.
Chemotherapy before surgery
1
Our approach
We follow the SIOP approach, with vincristine and actinomycin D for four weeks to shrink the tumor and lower the risk of rupture during surgery.
Children with syndromes linked to Wilms tumor, such as WAGR, Denys-Drash or Beckwith-Wiedemann, need ultrasound screening every three months during early childhood.
The Wilms tumor operation
Keyhole against open Wilms nephrectomy, 9 studies
Outcome
Keyhole
Open
Tumor spill and positive margins
Similar
Similar
Recurrence and survival
Similar
Similar
Lymph nodes sampled
Three fewer
More
Hospital stay
About one day shorter
Longer
1
Radical nephrectomy
The surgeon removes the kidney with the tumor, its fat and ureter in one piece, without breaking the capsule, and samples lymph nodes along the aorta and vena cava for staging.
Most Wilms tumors are removed through a wide transverse cut in the upper abdomen. Keyhole surgery suits small, centrally located tumors after chemotherapy, and an earlier American review warned that keyhole series sampled too few lymph nodes and selected only small tumors (Malek and colleagues, Journal of Pediatric Surgery, 2020). Lymph node sampling decides the stage and the treatment after surgery.
Will our child need radiotherapy?
Stage, histology and lymph node findings decide. Many children with early stage tumors receive chemotherapy only. Radiotherapy, when needed, starts within two weeks of surgery and is planned at our radiation oncology unit.
Saving part of a kidney with a tumor
1
Nephron-sparing surgery
Removing the tumor with a rim of normal tissue and keeping the rest of the kidney. Standard for tumors in both kidneys, in a single kidney and in children with syndromes.
A review of 26 studies compared 657 children treated by partial nephrectomy with 10,322 treated by complete removal for Wilms tumor in one kidney. Survival and recurrence did not differ, and kidney function after partial nephrectomy was better (Li and colleagues, Pediatric Surgery International, 2024).
When we consider partial nephrectomy
Situation
Choice
Note
Tumors in both kidneys
Partial nephrectomy on both sides when possible
After six to twelve weeks of chemotherapy
Tumor in a single kidney
Partial nephrectomy
Avoids dialysis
Small polar tumor, one side
Selected cases
Needs clear margins
Partial nephrectomy for a one-sided tumor with a normal other kidney is chosen only when the tumor is small, at one pole, and complete removal is certain.
Each case is discussed at the pediatric tumor board with oncologists, radiologists and pathologists.
The day of surgery
A typical day
Step
Timing
Note
Arrival and checks
Morning
Numbing cream
Anesthesia
Parent present at induction
General anesthesia, local block
Surgery
One to two hours keyhole, two to four open
Longer for tumors
Recovery
One to two hours
Then the ward or intensive care
Fasting follows standard rules, solids six hours, breast milk four hours and clear fluids one hour before anesthesia.
Pain relief combines a local anesthetic block placed while the child sleeps with paracetamol and, after open surgery, an epidural or a pain pump. A urinary catheter stays in place for a day.
Recovery at home
Keyhole surgery for benign disease, back to nursery or school in one week.
Open surgery, two to three weeks off school.
No contact sport or climbing for four to six weeks after open surgery.
The scars are small after keyhole surgery and fade within a year.
Children eat and walk on the first day. Dissolving stitches need no removal, and short baths are fine after 48 hours.
Call us if you see
Sign
Possible cause
Action
Fever over 38.5 degrees
Infection
Call the same day
Little urine, swelling
Kidney strain or dehydration
Call at once
Wound redness or discharge
Wound infection
Send a photograph
Severe belly pain or vomiting
Bowel problem after surgery
Call at once
Life with one kidney
1
Lifelong checks
Blood pressure, urine protein and kidney function once a year for life, with the pediatric nephrologist and later the family doctor.
A Dutch study followed children with one kidney for 15 years and found signs of kidney injury, such as high blood pressure, protein in the urine or lower function, in 23 percent of Wilms tumor survivors and 54 percent of children with one kidney for other reasons (Mavinkurve-Groothuis and colleagues, Pediatric Nephrology, 2016). Early detection allows treatment that protects the remaining kidney.
Everyday advice
Protecting the remaining kidney
Area
Advice
Reason
Medicines
Avoid regular ibuprofen and similar drugs
They strain the kidney
Salt and weight
Normal diet, low salt, healthy weight
Blood pressure
Sport
Most sports are fine, discuss collision sports
Injury is rare
Talking with your child
Children notice scars and ask questions.
Simple words help at each age, a doctor took away a kidney that was making you ill and the other one works for both, and older children with one kidney can carry a small card or a note on their phone so that any doctor treating them later knows, while teenagers learn the reasons for yearly checks and take part in the visits themselves. Our psychologists support children treated for Wilms tumor and their brothers and sisters.
Pride in a scar helps too.
For families from abroad
Send ultrasound and nuclear scan reports, MRI or CT images, kidney function results and, for tumors, the chemotherapy given so far. Our team reviews them and proposes a plan before you travel.
For Wilms tumor, we coordinate chemotherapy before surgery either in Istanbul or with your home team using the same protocol.
1
Length of stay
Plan for five to seven days in Istanbul after keyhole nephrectomy for benign disease and two to three weeks for open or tumor surgery. Fitness to fly follows a wound check and normal kidney blood tests.
Children in Wilms treatment may stay for the full course of chemotherapy, or return home between phases.
One coordinator from the international patients office handles arrangements from the first message through discharge and answers the same WhatsApp number after you return. The office works in English, Arabic, French, Russian, Serbian, Romanian and Spanish and books interpreters for other languages, and it arranges the visa invitation letter, airport transfers, daily transport and accommodation near the hospital. Halal, vegetarian and diabetic meals, a prayer room on site, and a female physician on request wherever the rota allows.
2
After you return home
Blood pressure, urine and kidney blood tests continue with your local doctor, and we review results by video and message.
Cost
What a quote for nephrectomy in a child covers
Item
Included
Priced separately
Surgery
Surgeon, anesthesia, operating room, pathology
Second operations
Hospital
Ward stay as planned, intensive care when planned
Extra days
Aftercare
Medicines at discharge, video follow-up
Chemotherapy, radiotherapy
What changes the price
Keyhole surgery for a benign kidney costs less than open surgery for a tumor.
Factors that change the quote
Factor
Effect
Example
Diagnosis
Benign or tumor
Wilms needs staging and chemotherapy
Approach
Keyhole or open
Large tumors are removed open
Extra tests
Nuclear scans, MRI
When not done before travel
We send a written quote after reviewing reports and imaging, before you travel. Compare quotes for the same operation and check that follow-up is part of the plan.
Quotes for tumors
For Wilms tumor, the quote follows the plan the tumor board proposes and lists surgery, chemotherapy and any radiotherapy separately.
References
Mosa H, Giannettoni A, Patil K, et al. Pediatric nephrectomy, comparison of perioperative outcomes of three different minimally invasive and open approaches. J Laparoendosc Adv Surg Tech A. 2021;31(12):1466-1470.
Pio L, Bruno T, Godzinski J, et al. Comparison of open and minimally invasive nephrectomy for Wilms tumor, a systematic review and meta-analysis from the International Society of Pediatric Surgical Oncology. Pediatr Surg Int. 2025;41(1):117.
Malek MM, Behr CA, Aldrink JH, et al. Minimally invasive surgery for pediatric renal tumors, a systematic review by the APSA Cancer Committee. J Pediatr Surg. 2020;55(11):2251-2259.
Li S, Wang J, Li M, et al. Efficacy and late kidney effects of nephron-sparing surgery in the management of unilateral Wilms tumor, a systematic review and meta-analysis. Pediatr Surg Int. 2024;40(1):29.
Mavinkurve-Groothuis AMC, van de Kracht F, Westland R, et al. Long-term follow-up of blood pressure and glomerular filtration rate in patients with a solitary functioning kidney, a comparison between Wilms tumor survivors and nephrectomy for other reasons. Pediatr Nephrol. 2016;31(3):435-441.
Editor's note
Written by the Biruni Hospital medical editorial team. Reviewed by Assoc. Prof. Dr. Ayhan YAMAN, Pediatric Intensive Care.